A stroke is the sudden loss of neurological function from a vascular cause — either a blocked artery (ischemic) or a ruptured one (hemorrhagic). On USMLE Step 1, stroke rewards two linked skills: localizing the lesion from the deficit using vascular territories, and knowing the time-critical acute pathway. This guide connects the vessel to the deficit and lays out the systematic approach that Step 1 tests.
Evidence-based · For exam prep, not medical advice
update Updated October 2026
Date of last content change
Built by surgery and anesthesiology residents
Written for USMLE Step 1 · Free to read
bolt The 60-second version
A stroke is the sudden loss of neurological function from a vascular cause — either a blocked artery (ischemic) or a ruptured one (hemorrhagic). On USMLE Step 1, stroke rewards two linked skills: localizing the lesion from the deficit using vascular territories, and knowing the time-critical acute pathway.
check_circleIschemic stroke (~87%) is arterial occlusion (thrombotic or embolic); hemorrhagic (~13%) is a ruptured vessel (often hypertensive).
check_circleThe first test in any suspected stroke is a non-contrast head CT — to exclude hemorrhage before any thrombolytic is given.
check_circleACA → contralateral LEG weakness; MCA → contralateral face/arm weakness plus aphasia (dominant) or neglect (nondominant); PCA → contralateral homonymous hemianopia.
check_circleIV thrombolysis (alteplase/tenecteplase) is given within 4.5 hours of last known well in eligible patients.
check_circleMechanical thrombectomy treats large-vessel occlusions, in selected patients up to 24 hours.
check_circleA deficit that fully resolves without infarction is a transient ischemic attack (TIA) — a warning for future stroke.
target What you'll be able to do · aligned to USMLE Step 1 · Nervous System
PATHDistinguish ischemic from hemorrhagic stroke by mechanism, common causes, and initial imaging.
DXMap the anterior, middle, and posterior cerebral artery territories to their classic clinical deficits.
DXLocalize a stroke from the pattern of weakness, language, vision, and cortical signs.
RXOutline the acute pathway: non-contrast CT first, then thrombolysis and thrombectomy within their time windows.
How stroke is tested on Step 1
Step 1 stroke questions do two things: they give a deficit and ask you to localize the vessel, or they give a time course and ask for the next step. Occasionally they test the mechanism (embolic source, lacunar risk factors) or the sharp distinction between ischemic and hemorrhagic on initial management. A systematic approach — type, territory, timing — handles all of them.
workspace_premium The through-line
One artery, one territory, one syndrome. If you know which vessel is down, the deficit and the next step follow.
Ischemic vs hemorrhagic
The first fork is mechanism, because it changes the very first management step. Ischemic strokes are occlusions; hemorrhagic strokes are bleeds, and giving a thrombolytic to a bleed is catastrophic — which is why imaging comes first.
Two mechanisms. Ischemic stroke is an occluded artery (thrombotic or embolic) causing infarction; hemorrhagic stroke is a ruptured vessel, most often from chronic hypertension or an aneurysm.
Feature
Ischemic
Hemorrhagic
Mechanism
Arterial occlusion
Vessel rupture / bleeding
Common causes
Thrombosis, cardioembolism (AF)
Hypertension, aneurysm, AVM
First test
Non-contrast CT (to exclude bleed)
Non-contrast CT (shows blood)
Acute treatment
Thrombolysis / thrombectomy
Reverse anticoagulation, control BP
Both start with a non-contrast head CT; the result decides whether thrombolysis is even possible.
Within ischemic stroke, Step 1 distinguishes two mechanisms because they point to different sources. A thrombotic stroke forms on a ruptured atherosclerotic plaque in a large artery — the same process as coronary disease — and tends to evolve over minutes. An embolic stroke is a clot that traveled from elsewhere, most classically from the left atrium in atrial fibrillation, and tends to be sudden and maximal at onset. A third pattern, the lacunar stroke, comes from lipohyalinosis of small penetrating arteries driven by chronic hypertension and diabetes. Recognizing the mechanism is not academic: it changes the secondary-prevention answer, from a statin and antiplatelet for atherosclerosis to anticoagulation for a cardioembolic source.
Vascular territories and deficits
Localization is the core Step 1 skill. Each major cerebral artery supplies a defined region, and infarction there produces a stereotyped deficit.
Territories → deficits. ACA supplies the medial cortex (leg); MCA supplies the lateral cortex (face/arm, and the language or attention areas); PCA supplies the occipital lobe (vision).
Artery
Territory
Classic deficit
ACA
Medial frontal/parietal
Contralateral leg > arm weakness
MCA
Lateral hemisphere
Contralateral face/arm weakness; aphasia (dominant) or neglect (nondominant)
PCA
Occipital lobe
Contralateral homonymous hemianopia
Lacunar (small vessel)
Internal capsule / pons
Pure motor or pure sensory stroke
The homunculus explains ACA vs MCA: the leg is medial (ACA), the face and arm are lateral (MCA).
Localizing from the exam
Read the deficit as a map. Weakness that is worse in the leg points to the ACA; face-and-arm weakness with a language or attention problem points to the MCA; an isolated visual-field cut points to the PCA.
functions Worked example — localize the lesion
A 70-year-old with atrial fibrillation suddenly develops right-sided face and arm weakness and cannot produce fluent speech. Which artery is affected, and on which side?
Face and arm (not leg) weakness points to the MCA territory, not the ACA.
A language deficit (aphasia) localizes to the dominant (usually left) hemisphere.
Motor deficits are contralateral, so right-sided weakness means a left-hemisphere lesion.
Answer. A left middle cerebral artery (MCA) stroke — most likely cardioembolic given the atrial fibrillation. The combination of contralateral face/arm weakness plus aphasia is the classic dominant-MCA syndrome.
error Common trap
A “pure motor” hemiparesis with no cortical signs (no aphasia, no neglect, no visual loss) suggests a lacunar stroke of the internal capsule — a small-vessel disease of chronic hypertension and diabetes, not a large-artery syndrome.
The acute pathway and timing
Stroke management is a race against neuronal death, but the sequence is fixed: image first, then treat within the window.
Time is brain. Establish the last-known-well time, get a non-contrast CT to exclude hemorrhage, give IV thrombolysis within 4.5 hours if eligible, and consider thrombectomy for a large-vessel occlusion up to 24 hours in selected patients.
Non-contrast CT first — it rules out hemorrhage; early ischemia is often invisible, which is the point.
IV thrombolysis within 4.5 hours of last known well, if no contraindication.
Mechanical thrombectomy for large-vessel occlusion, in selected patients up to 24 hours.
TIA: symptoms resolve without infarction — treat as a warning and work up the cause.
The reason imaging must come first is that the treatments are opposite. In a confirmed ischemic stroke you want to restore flow, so you give a thrombolytic or pull the clot; in a hemorrhage you must stop bleeding, so you reverse anticoagulation and control blood pressure. A thrombolytic given to a bleed is lethal, which is why the non-contrast CT is non-negotiable before any clot-dissolving drug, and why active bleeding, recent surgery, and very high blood pressure are contraindications to thrombolysis.
How to study it — and the traps to avoid
Stroke rewards a fixed sequence: type, territory, timing — plus the homunculus to tie arteries to deficits.
Separate ischemic from hemorrhagic and remember the non-contrast CT comes first, always.
Memorize the ACA (leg), MCA (face/arm + aphasia/neglect), and PCA (vision) map.
Recognize lacunar syndromes (pure motor/sensory) and their small-vessel risk factors.
Know the time windows: 4.5 hours for thrombolysis, up to 24 hours for select thrombectomy.
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
12
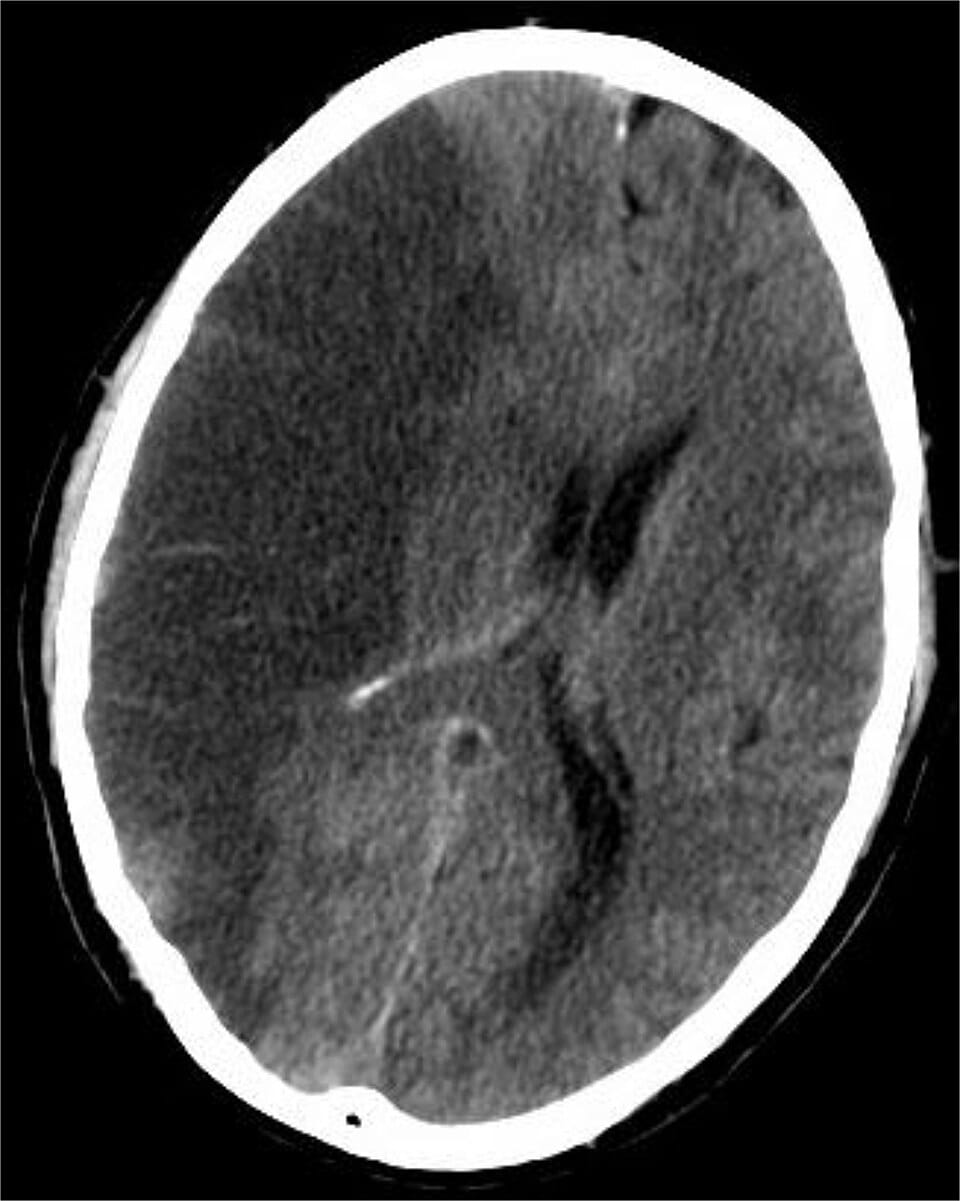
A 68-year-old man with atrial fibrillation not on anticoagulation presents with acute-onset left-sided weakness and aphasia. CT head performed within 2 hours of symptom onset, image shown below. Which of the following best explains the pathophysiology of acute arterial ischemia in the brain and the time-dependent relationship between vascular occlusion, tissue ischemia, and the potential for thrombolytic intervention to salvage ischemic penumbra?
Lucien Monfils, CC BY-SA 4.0 <https://creativecommons.org/licenses/by-sa/4.0>, via Wikimedia Commons
Answer: B. Acute arterial ischemia creates a gradient of severity: the ischemic core (innermost region receiving <10–20% of normal perfusion) undergoes irreversible necrosis within minutes; surrounding this core is the ischemic penumbra (region receiving 20–40% of normal perfusion), where neurons are dysfunctional but viable. The penumbra exists in a precarious state, dependent on collateral circulation and vulnerable to secondary injury from edema, metabolic derangements, and oxidative stress. Thrombolytic agents (alteplase) restore flow and can salvage penumbral tissue if administered within a narrow therapeutic window, typically 3–4.5 hours (or up to 24 hours in selected patients with perfusion imaging evidence of salvageable penumbra). Delays beyond this window result in progression of penumbra to infarction as collateral flow fails and secondary injury cascades are activated. Option A incorrectly implies no salvageable tissue exists; options C, D, and E invoke incorrect mechanisms (vasospasm protection, narrow caspase window, committed penumbra).
Source: Savitz, S. I., & Fisher, M. (2019). Future of neuroprotection for acute stroke in the aftermath of the STAIR trials. Journal of Cerebral Blood Flow & Metabolism, 39(10).
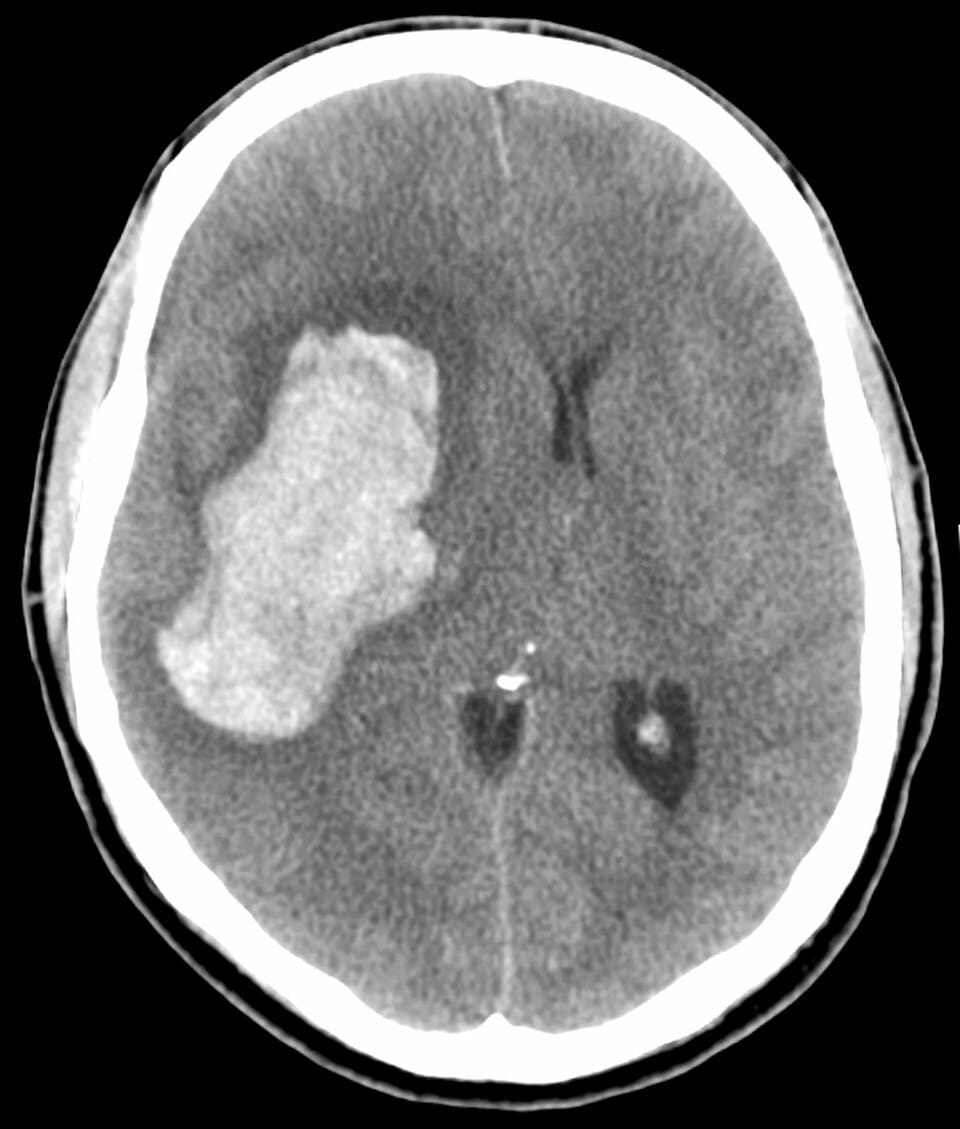
A 72-year-old man with poorly controlled hypertension (BP 180/110 mmHg) presents with sudden-onset severe headache and focal neurologic deficit. CT head is shown below. Which of the following best explains the pathophysiology of hypertensive intracerebral hemorrhage and the anatomic predilection for deep brain structures in this patient?
James Heilman, MD, CC BY-SA 4.0 <https://creativecommons.org/licenses/by-sa/4.0>, via Wikimedia Commons
Answer: B. Chronic hypertension triggers medial smooth muscle hypertrophy and lipohyalinosis (hyaline degeneration) in small penetrating arteries, particularly the lenticulostriate arteries arising from the MCA and the pontine perforating arteries arising from the basilar artery. These lipohyalinotic vessels are fragile and prone to rupture, especially during acute blood pressure surges. The basal ganglia (putamen, globus pallidus, internal capsule) and pons are the classic locations for hypertensive hemorrhage because they are supplied by these susceptible small penetrating vessels. Histologically, hypertensive hemorrhages show fibrinoid necrosis of vessel walls, lipohyalinosis, and rupture. Option A incorrectly attributes hemorrhage to aneurysm formation; option C confuses vasospasm mechanisms with hemorrhage; options D and E invoke incorrect mechanisms (RBC osmotic lysis, BBB permeability alone).
Source: Qureshi, A. I., & Qureshi, M. H. (2018). Acute hypertensive response in patients with intracerebral hemorrhage pathophysiology and treatment. Journal of Cerebral Blood Flow and Metabolism, 38(9).
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
When is 'last known well' used in stroke management?expand_more
Stroke onset time is defined as 'last known well' — when the patient was last confirmed to be at baseline. For wake-up strokes (patient wakes with deficits), onset time is the last time they were seen normal before sleep. This is critical for tPA eligibility: if last known well was >4.5 hours ago, standard IV tPA is contraindicated. MRI-guided selection (DWI/FLAIR mismatch) can identify wake-up stroke patients who may benefit from thrombolysis.
What is the difference between TIA and stroke?expand_more
Traditionally, TIA was defined by symptom resolution within 24 hours. The modern definition (tissue-based): TIA = transient neurological symptoms with NO infarction on diffusion-weighted MRI. Stroke = brain infarction confirmed on MRI regardless of symptom duration. This matters because some clinically 'brief' events show DWI lesions and should be managed as stroke. ABCD2 score helps risk-stratify TIA for early stroke risk.
What is the target blood pressure in ischemic stroke before tPA?expand_more
For tPA eligibility, BP must be ≤185/110 mmHg before administration. Labetalol IV (10–20 mg) or nicardipine IV drip are the typical agents to lower BP acutely. If BP cannot be lowered below this threshold, tPA should be withheld. After tPA, maintain BP <180/105 for at least 24 hours to reduce hemorrhagic transformation risk.
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.