How bipolar disorder is tested on Step 1
Duration and severity separate mania from hypomania.
Lithium
Effective, but dosing depends on kidney handling of sodium.
- Interactions: thiazides cause volume loss, and the proximal tubule then reabsorbs more sodium and lithium. ACE inhibitors, NSAIDs, and dehydration also raise levels.
- Monitoring: serum lithium levels, kidney function, TSH, and calcium (lithium can cause hyperparathyroidism).
- Nephrogenic DI from lithium: amiloride blocks lithium entry into collecting duct cells.
Other mood stabilizers
Choose by phase of illness and side effect profile.
| Drug | Best use | Key adverse effects |
|---|---|---|
| Valproate | Acute mania, rapid cycling | Hepatotoxicity, pancreatitis, weight gain, neural tube defects |
| Carbamazepine | Mania | Agranulocytosis, SIADH, Stevens-Johnson syndrome, CYP induction |
| Lamotrigine | Bipolar depression and maintenance | Stevens-Johnson syndrome |
| Atypical antipsychotics (quetiapine, olanzapine, aripiprazole) | Acute mania; some for bipolar depression | Metabolic syndrome, sedation |
Antidepressant monotherapy is avoided because it can switch patients into mania.
Related diagnoses
Rule out medical and substance causes.
- Cyclothymic disorder: at least 2 years of hypomanic and depressive symptoms that do not meet full criteria.
- Substance- or medication-induced mania: stimulants, corticosteroids, and antidepressants.
- Medical causes: hyperthyroidism, frontal lobe lesions, and multiple sclerosis can mimic mania.
Worked example
Find the interaction.
functions Worked example — new tremor and confusion
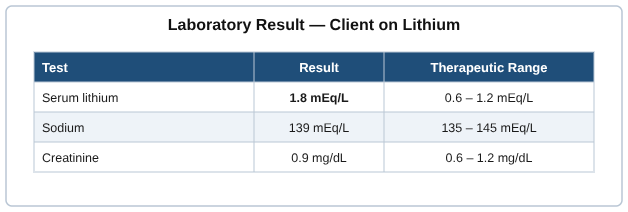
A patient stable on lithium for years is started on hydrochlorothiazide for blood pressure. Two weeks later they have vomiting, a coarse tremor, unsteady gait, and confusion. What happened?
- Coarse tremor, ataxia, GI upset, and confusion are signs of lithium toxicity.
- Thiazides cause mild volume depletion.
- The proximal tubule responds by reabsorbing more sodium and, with it, lithium.
- Stop the thiazide and lithium, give fluids, and consider hemodialysis if severe.
Answer. Lithium toxicity caused by thiazide-induced increase in proximal lithium reabsorption.