How the thyroid is tested on Step 1
Start with synthesis and the drugs that block each step.
| Pattern | TSH | Free T4 | Example |
|---|---|---|---|
| Primary hypothyroidism | ↑ | ↓ | Hashimoto thyroiditis |
| Subclinical hypothyroidism | ↑ | Normal | Early Hashimoto |
| Primary hyperthyroidism | ↓ | ↑ | Graves disease, toxic nodule |
| Central hypothyroidism | ↓ or normal | ↓ | Pituitary disease |
| TSH-secreting adenoma | ↑ or normal | ↑ | Rare pituitary tumor |
TSH is the best screening test in most patients.
Hyperthyroidism and hypothyroidism
Autoimmunity causes most of both.
- Subacute granulomatous (de Quervain) thyroiditis: painful, tender thyroid after a viral illness; high ESR; transient hyperthyroidism, then hypothyroidism; low uptake.
- Painless and postpartum thyroiditis: lymphocytic, transient, low uptake.
- Toxic multinodular goiter and toxic adenoma: TSH-independent nodules; patchy or focal uptake.
- Congenital hypothyroidism: lethargy, poor feeding, big tongue, umbilical hernia, prolonged jaundice; detected by newborn screening.
- Drugs: lithium and amiodarone can cause hypothyroidism; amiodarone can also cause hyperthyroidism.
Thyroid storm and treatment
Block the effects, synthesis, release, and conversion.
- Thyroid storm: fever, tachycardia or atrial fibrillation, agitation, and vomiting after a trigger (surgery, infection, iodine load). Treat with propranolol, PTU (or methimazole), then iodine solution, and corticosteroids.
- Antithyroid drugs: methimazole is preferred except in the first trimester (teratogenic) and storm; PTU can cause liver failure; both can cause agranulocytosis.
- Levothyroxine: treats hypothyroidism; overtreatment causes atrial fibrillation and bone loss.
- Myxedema coma: severe hypothyroidism with hypothermia, low sodium, and confusion; IV levothyroxine and steroids.
Thyroid cancers
Histology, spread, and genetic associations.
| Cancer | Key features | Spread and associations |
|---|---|---|
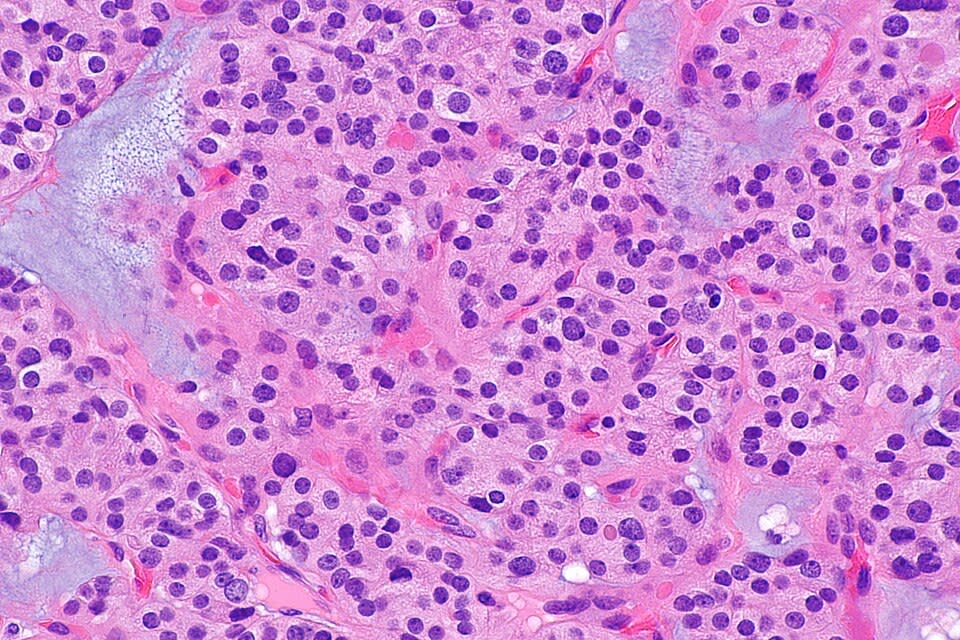
| Papillary (most common) | Ground-glass "Orphan Annie" nuclei, nuclear grooves, psammoma bodies | Lymphatic; radiation exposure; RET/PTC, BRAF; excellent prognosis |
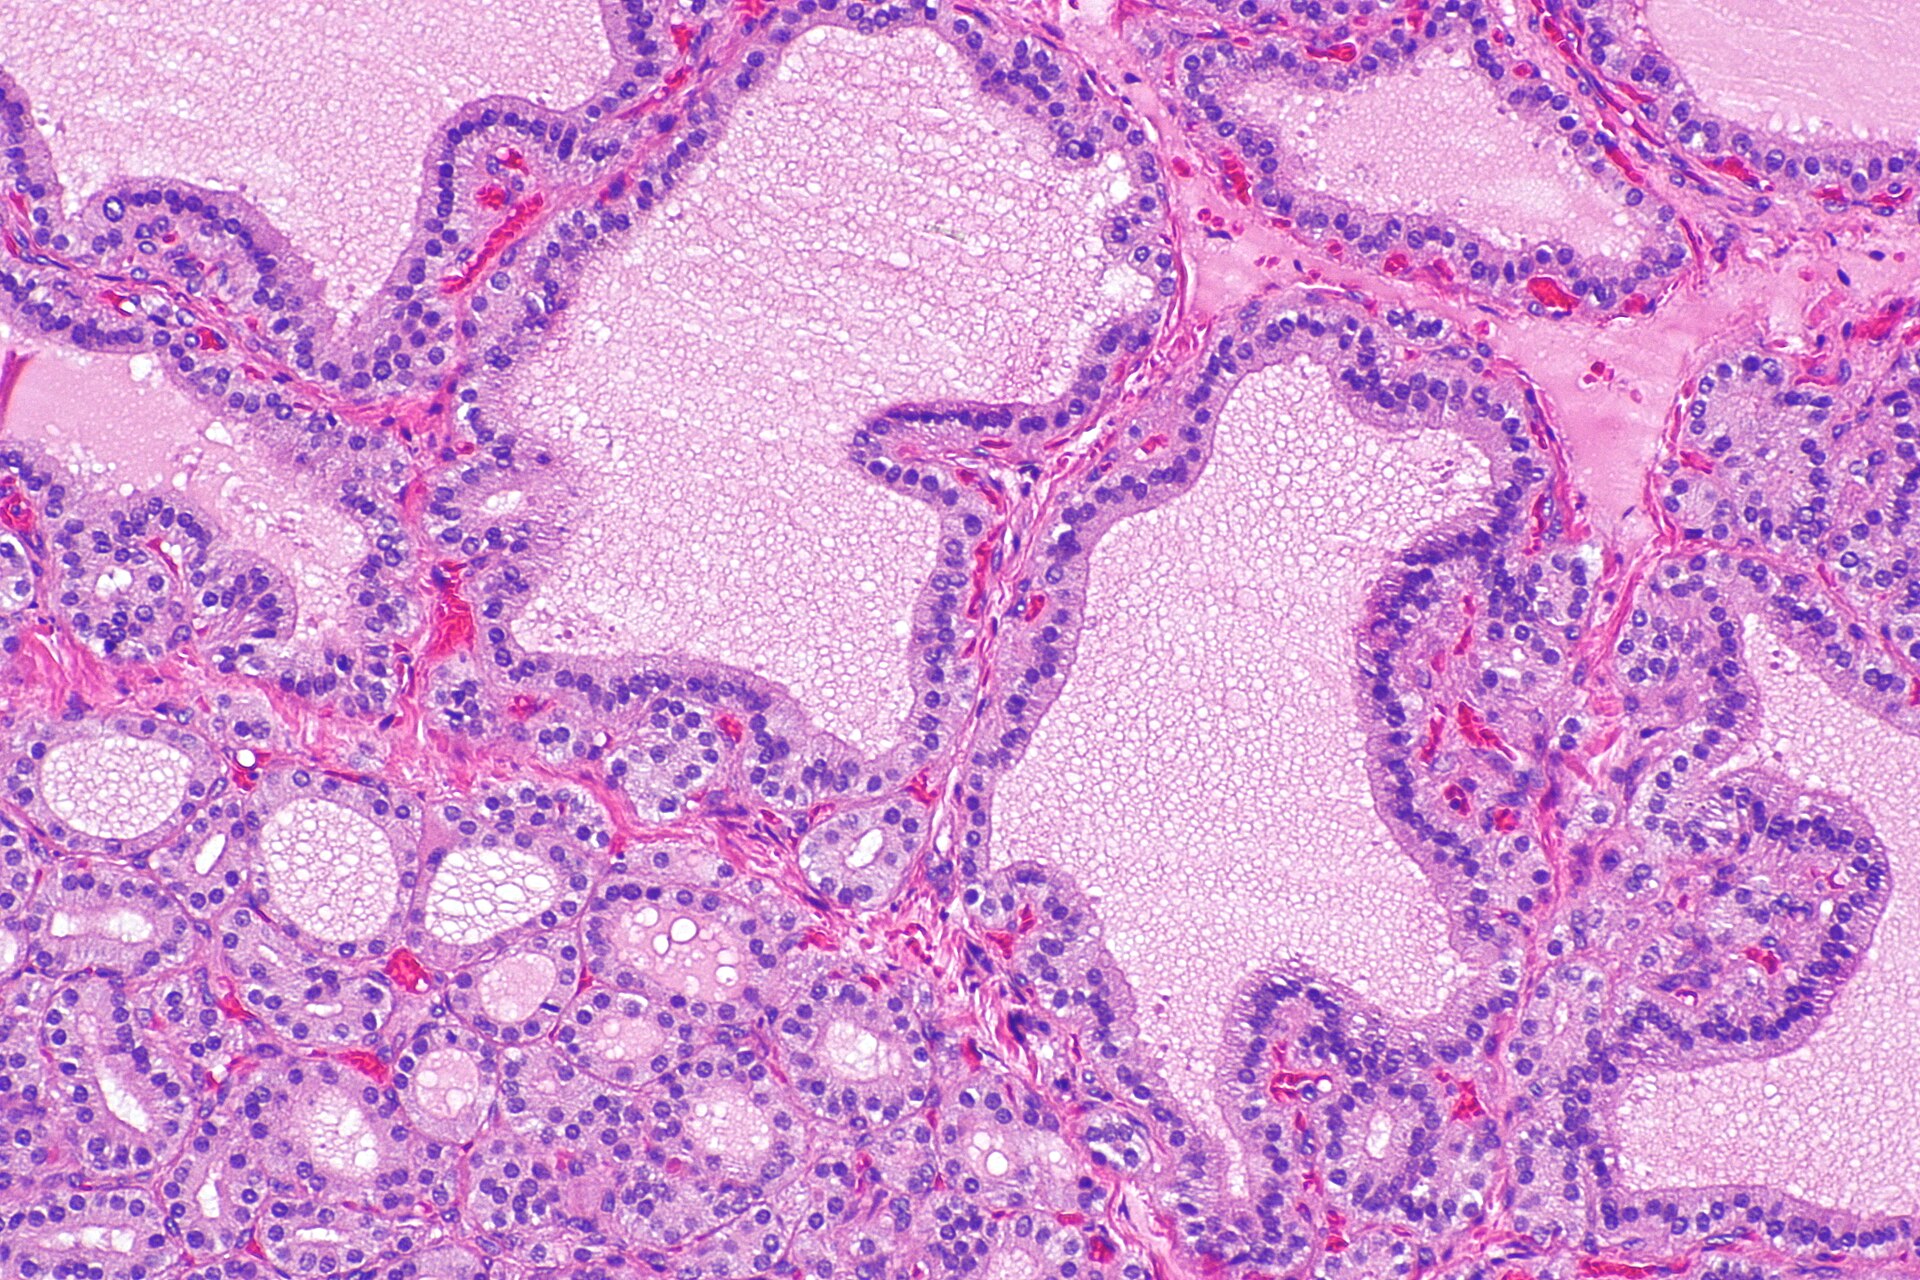
| Follicular | Invades the capsule or vessels | Bloodstream (bone, lung); RAS |
| Medullary | C cells; calcitonin; amyloid stroma | MEN2A and 2B (RET) |
| Anaplastic | Undifferentiated; older adults | Rapid local invasion; very poor prognosis; TP53 |
| Lymphoma | B-cell; rapidly enlarging gland | Hashimoto thyroiditis |
Thyroid nodules are evaluated with TSH, ultrasound, and fine-needle aspiration.
Worked example
Find the antibody.
functions Worked example — palpitations and bulging eyes
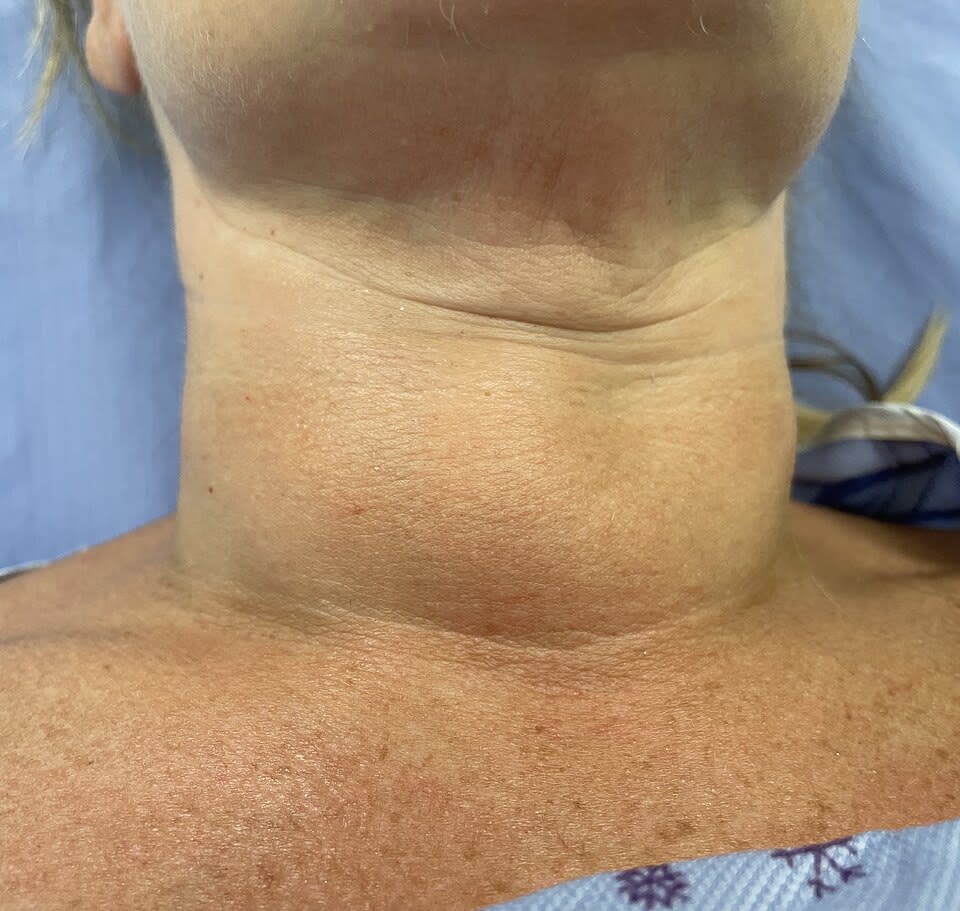
A 32-year-old has weight loss, heat intolerance, palpitations, a diffuse non-tender goiter, protruding eyes, and thickened skin over the shins. TSH is low and free T4 high. What mechanism causes the disease?
- Low TSH with high T4 means primary hyperthyroidism.
- Exophthalmos and pretibial myxedema are specific to Graves disease.
- Antibodies stimulate the TSH receptor on thyroid cells, orbital fibroblasts, and dermal fibroblasts.
- This is a type II hypersensitivity in which the antibody activates rather than destroys its target.
Answer. Graves disease from TSH receptor–stimulating antibodies.