Diabetes mellitus is a group of disorders of chronic hyperglycemia caused by defects in insulin secretion, insulin action, or both. It is one of the densest integration topics on USMLE Step 1 — spanning endocrine physiology, the pathophysiology of type 1 versus type 2, acute metabolic emergencies, and a signature set of chronic complications. This guide builds the disease from the physiology of glucose regulation up through the diagnosis, the emergencies, and the complications most likely to appear in a vignette.
Evidence-based · For exam prep, not medical advice
update Updated October 2026
Date of last content change
Built by surgery and anesthesiology residents
Written for USMLE Step 1 · Free to read
bolt The 60-second version
Diabetes mellitus is a group of disorders of chronic hyperglycemia caused by defects in insulin secretion, insulin action, or both.
check_circleInsulin from pancreatic β cells lowers blood glucose (promotes uptake and storage); glucagon from α cells raises it (glycogenolysis and gluconeogenesis).
check_circleDiagnosis: fasting glucose ≥126 mg/dL, 2-h OGTT ≥200, HbA1c ≥6.5%, or random ≥200 with symptoms.
check_circleHbA1c reflects average glycemia over ~3 months (the lifespan of a red cell).
check_circleDKA (usually type 1) = hyperglycemia + ketoacidosis; HHS (usually type 2) = severe hyperglycemia + hyperosmolarity without significant ketosis.
check_circleChronic complications are microvascular (retinopathy, nephropathy, neuropathy) and macrovascular (coronary disease, stroke, peripheral artery disease).
target What you'll be able to do · aligned to USMLE Step 1 · Endocrine System
PHYSDescribe how insulin (β cells) and glucagon (α cells) regulate blood glucose through opposing negative feedback.
PATHContrast the pathophysiology of type 1 (autoimmune β-cell destruction) and type 2 (insulin resistance with relative deficiency) diabetes.
DXApply the diagnostic criteria for diabetes (fasting glucose, 2-hour OGTT, HbA1c, random glucose).
DXDistinguish diabetic ketoacidosis from the hyperosmolar hyperglycemic state, and list the chronic micro- and macrovascular complications.
How diabetes is tested on Step 1
Step 1 diabetes questions cluster into four themes: the physiology of insulin and glucagon, distinguishing type 1 from type 2, recognizing the acute emergencies (DKA and HHS), and predicting chronic complications. Vignettes often give a body habitus and time course, an HbA1c or glucose value, or an acute presentation and ask for the mechanism, the diagnosis, or the complication.
workspace_premium The through-line
Everything follows from insulin: too little (or ineffective) insulin means cells starve amid high blood glucose, driving the osmotic symptoms, the ketosis, and — over years — the vascular complications.
The physiology: insulin, glucagon, and glucose
Blood glucose is held in a narrow range by two opposing pancreatic hormones. After a meal, rising glucose triggers β cells to release insulin, which drives glucose into muscle and fat and promotes storage as glycogen and fat, lowering blood glucose. During fasting, α cells release glucagon, which mobilizes hepatic glucose through glycogenolysis and gluconeogenesis, raising it.
Glucose homeostasis. Insulin (β cells) lowers blood glucose by promoting uptake and storage; glucagon (α cells) raises it by mobilizing hepatic glucose. The two loops keep glucose near 70–110 mg/dL.
Insulin is the body’s only major glucose-lowering hormone, which is why its absence is so catastrophic. It is also anabolic across fuels — it promotes lipogenesis and inhibits lipolysis. When insulin is absent or ineffective, unrestrained lipolysis floods the liver with free fatty acids that are converted to ketone bodies, the biochemical basis of diabetic ketoacidosis. Understanding insulin as both a glucose-lowering and an anti-lipolytic hormone explains why type 1 patients, who make essentially none, are the ones who develop ketoacidosis.
Type 1 vs type 2
The two major forms share hyperglycemia but differ fundamentally in mechanism, and Step 1 leans on that contrast.
Two mechanisms. Type 1 is autoimmune destruction of β cells (absolute insulin deficiency); type 2 is peripheral insulin resistance with a relative deficiency that worsens as β cells fail.
Feature
Type 1
Type 2
Mechanism
Autoimmune β-cell destruction
Insulin resistance + relative deficiency
Insulin
Absolute deficiency
Normal/high early, falls later
Typical onset
Children/young, lean
Adults, obese, gradual
Ketosis
Prone (DKA)
Uncommon (HHS instead)
Autoantibodies
Present (e.g., anti-GAD)
Absent
Type 1 = no insulin (autoimmune); type 2 = insulin present but resisted, with progressive β-cell failure.
Diagnosis
Diabetes is diagnosed by any of several glucose-based thresholds; HbA1c adds a measure of chronic control.
Test
Diabetes threshold
Fasting plasma glucose
≥126 mg/dL
2-hour OGTT
≥200 mg/dL
HbA1c
≥6.5%
Random glucose + symptoms
≥200 mg/dL
HbA1c reflects average glycemia over ~3 months (the red-cell lifespan), so it is unaffected by a single meal.
functions Worked example — make the diagnosis
An asymptomatic 55-year-old with obesity has a fasting glucose of 118 mg/dL on two occasions and an HbA1c of 6.7%. What is the diagnosis?
Fasting 118 mg/dL is in the prediabetes range (100–125), not diabetic on its own.
HbA1c ≥6.5% meets the diabetes threshold.
A single diagnostic-range result is typically confirmed on repeat testing.
Answer. Diabetes mellitus (type 2, given the phenotype) by the HbA1c criterion — the HbA1c of 6.7% exceeds 6.5%, and it should be confirmed with repeat testing.
Acute emergencies: DKA vs HHS
Two hyperglycemic emergencies are heavily tested and easily confused.
Feature
DKA
HHS
Usual type
Type 1
Type 2
Glucose
High (often 300–600)
Very high (often >600)
Ketoacidosis
Yes (anion-gap acidosis)
Minimal/absent
Osmolality
Elevated
Markedly elevated
Hallmark
Kussmaul breathing, fruity breath
Profound dehydration, ΔMS
Both are treated with fluids, insulin, and careful potassium repletion; DKA is defined by the ketoacidosis, HHS by extreme hyperosmolarity.
error Common trap
In DKA, total-body potassium is depleted even when the serum value looks normal or high — insulin therapy drives K⁺ into cells and can precipitate dangerous hypokalemia, so potassium must be monitored and replaced.
Chronic complications
Years of hyperglycemia damage vessels in two patterns that account for most diabetic morbidity.
Tight glycemic control chiefly reduces microvascular complications.
Step 1 often probes the biochemistry behind these complications. Persistently high glucose damages tissues through several mechanisms worth knowing by name: nonenzymatic glycation of proteins forms advanced glycation end-products that stiffen and injure vessel walls (and, in hemoglobin, produce the HbA1c we measure); and in tissues that take up glucose independent of insulin — the lens, retina, kidney, and Schwann cells — excess glucose is shunted through the polyol pathway to sorbitol, whose osmotic accumulation contributes to cataracts and neuropathy. The classic renal lesion, nodular glomerulosclerosis (Kimmelstiel–Wilson nodules), is a favorite image, and the earliest clinical sign of diabetic nephropathy is moderately increased albuminuria. Because these processes are driven by cumulative glucose exposure, they explain why long-term control — tracked by HbA1c — matters more than any single reading.
How to study it — and the traps to avoid
Diabetes rewards holding the whole arc in mind: physiology → type 1 vs type 2 → diagnosis → emergencies → complications.
Anchor to insulin: what it does normally, and what its absence or resistance causes.
Memorize the diagnostic cutoffs and what HbA1c represents (3-month average).
Separate DKA (type 1, ketoacidosis) from HHS (type 2, hyperosmolar) and watch potassium in DKA.
Group complications as microvascular vs macrovascular.
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
123
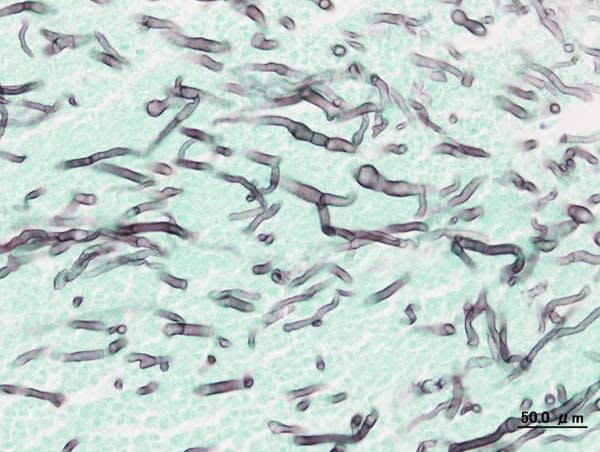
A 42-year-old man with diabetes mellitus presents with persistent fever, hemoptysis, and dyspnea. Chest CT shows multiple nodular infiltrates with evidence of cavitation and surrounding consolidation in the upper lobes bilaterally. Bronchoscopic lung biopsy shows an angioinvasive fungus, pictured below. Which of the following best explains the pathophysiology of the fungus and how angioinvasion leads to hemorrhage and hemoptysis in this immunocompromised host?
User:KGH, CC BY-SA 3.0 <http://creativecommons.org/licenses/by-sa/3.0/>, via Wikimedia Commons
Answer: B. Invasive aspergillosis, predominantly caused by Aspergillus fumigatus, is a life-threatening opportunistic infection in severely immunocompromised hosts, including those with prolonged neutropenia, advanced HIV/AIDS, organ transplant recipients, or those on immunosuppressive therapy. The pathophysiology centers on the angioinvasive properties of Aspergillus hyphae. Unlike saprophytic Aspergillus colonization (aspergilloma, a fungal ball in pre-existing cavities) or allergic bronchopulmonary aspergillosis (ABPA, an IgE-mediated hypersensitivity response), invasive aspergillosis is characterized by direct fungal invasion through pulmonary tissue and vascular invasion. The Aspergillus hyphae have specific mechanisms enabling angioinvasion: they produce proteases and toxins that facilitate penetration through tissue barriers, and they directly invade through the walls of pulmonary capillaries and arteries. This vascular invasion causes endothelial damage, thrombosis within invaded vessels, and rupture of the vessel wall. The consequences are hemorrhage into the alveolar space (producing hemoptysis and hemoptysis-related respiratory distress), tissue infarction distal to thrombosed vessels (producing nodular infiltrates and cavitation from necrosis), and dissemination to other organs (producing extrapulmonary aspergillosis). The histologic hallmark is the demonstration of fungal hyphae within vessel walls, distinguishing invasive from other forms of aspergillosis. The characteristic 45-degree angle branching and fine, regular septations of Aspergillus hyphae are visible on histology. Clinical risk factors include prolonged neutropenia (CD4 <50 cells/µL in HIV, or neutrophil count <500/µL), hematologic malignancies, and organ transplantation. Diagnosis requires histologic demonstration of angioinvasion; positive cultures alone are insufficient. Option A incorrectly implies superficial colonization without vascular invasion; option C overemphasizes allergic mechanisms; options D and E invoke incorrect mechanisms (toxin-induced apoptosis, immune-mediated neutrophil injury).
Source: Thompson, G. R., & Young, J. H. (2021). Aspergillus infections. New England Journal of Medicine, 385(16).
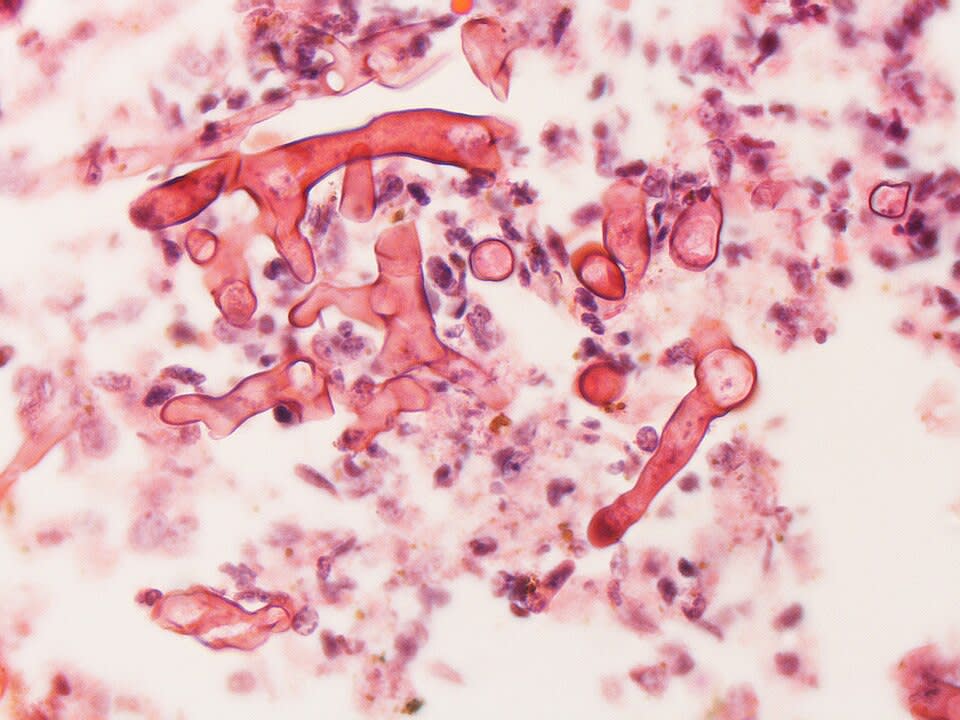
A 52-year-old man with poorly controlled diabetes presents in diabetic ketoacidosis with facial pain, a black necrotic eschar on the hard palate, and periorbital swelling. A biopsy of the necrotic tissue was done, and the photomicrograph is shown below. This patient's infection is most strongly predisposed by which of the following features of his underlying metabolic state?
Yale Rosen, CC BY-SA 2.0 <https://creativecommons.org/licenses/by-sa/2.0>, via Wikimedia Commons
Answer: E. Mucormycosis is strongly associated with diabetic ketoacidosis because hyperglycemia and acidosis impair neutrophil chemotaxis and phagocytic killing, crippling the primary innate immune defense against these ubiquitous environmental molds, while the acidic, hyperglycemic environment simultaneously increases the availability of free iron by reducing transferrin's iron-binding capacity, providing an essential growth nutrient for the fungus. The broad, ribbon-like, pauci-septate hyphae with wide-angle branching and prominent angioinvasion seen on biopsy reflect the organism's characteristic morphology and its propensity for vascular invasion and tissue infarction, producing the black necrotic eschar seen clinically. Hyphal septation is a fixed structural feature of the organism rather than a glucose-dependent trait, and the pathogenesis involves an innate immune defect rather than reactivation of latent infection or a primary T-cell defect.
Source: Cornely, O. A., et al. (2019). Global guideline for the diagnosis and management of mucormycosis. The Lancet Infectious Diseases, 19(12).
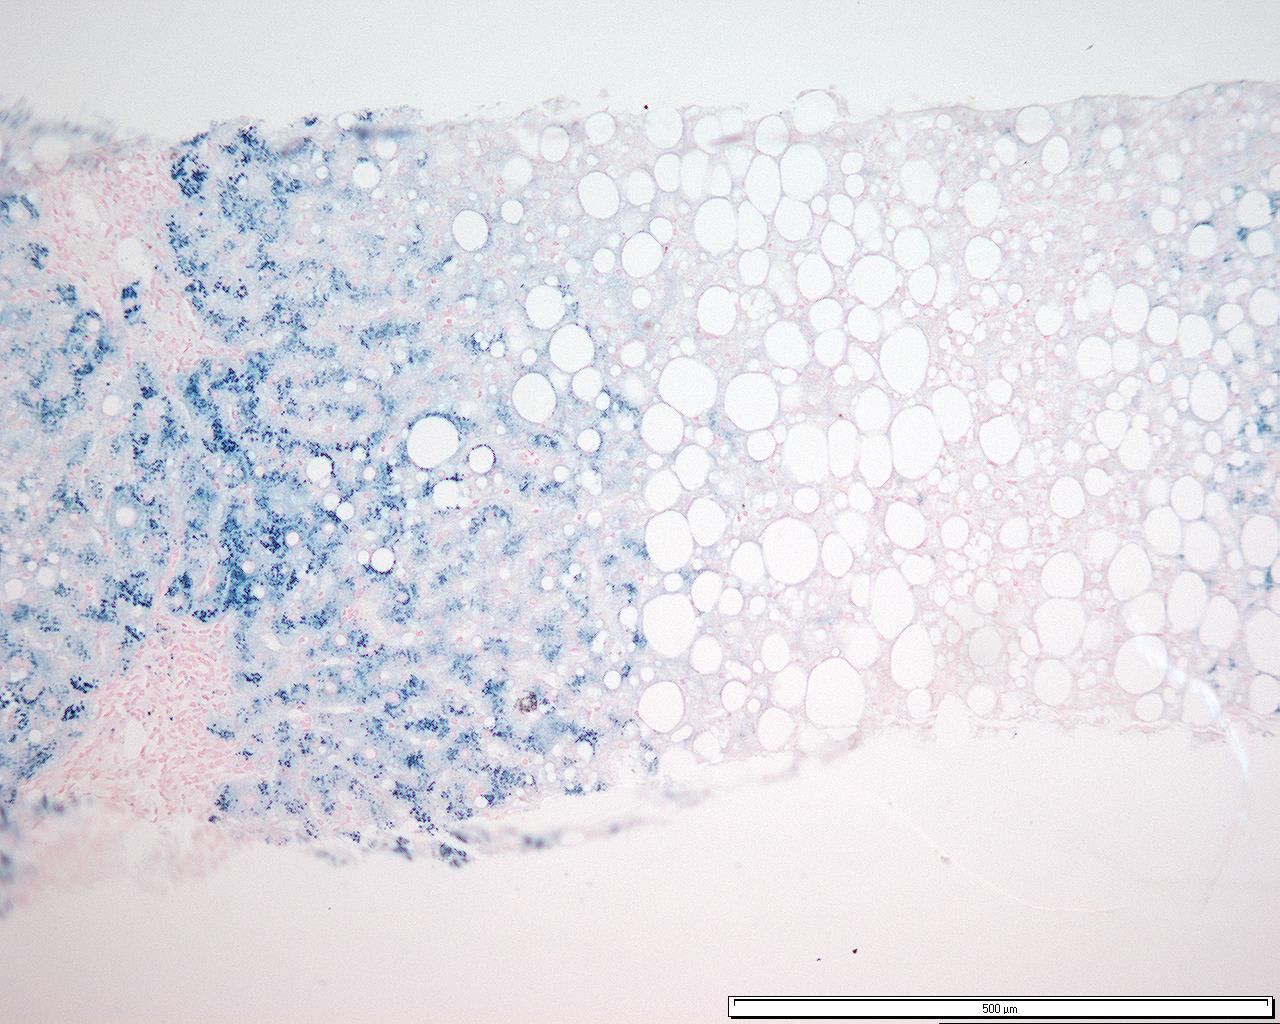
A 52-year-old man presents with fatigue, new-onset diabetes, bronze skin discoloration, and arthralgia of the second and third metacarpophalangeal joints. Liver biopsy was done and a photomicrograph is shown below stained with blue with Prussian blue. Genetic testing reveals a C282Y mutation in HFE. Which of the following best explains how this mutation leads to systemic iron overload?
Mathew, J et al, CC BY 3.0 <https://creativecommons.org/licenses/by/3.0>, via Wikimedia Commons
Answer: E. In HFE-associated hereditary hemochromatosis, the mutant HFE protein impairs hepatocyte sensing of iron stores, resulting in inappropriately low hepcidin production; because hepcidin normally binds and degrades ferroportin on enterocytes and macrophages to limit iron export, its deficiency allows unrestrained iron absorption and release into the circulation, producing progressive parenchymal iron deposition in the liver, pancreas, skin, joints, and heart. This hepcidin-ferroportin axis is the central regulatory mechanism disrupted in this disease, distinguishing it from the fabricated mechanisms describing direct enterocyte transporter overexpression, ferritin membrane leakage, macrophage transporter overexpression, or a shared copper-iron transport defect, none of which reflect the established pathophysiology of HFE-related iron overload.
Source: Powell, L. W., et al. (2016). Haemochromatosis. The Lancet, 388(10058).
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
What is the A1c target for most diabetic patients?expand_more
The ADA recommends A1c <7.0% for most non-pregnant adults with diabetes. Less stringent targets (<8.0%) are appropriate for older patients, those with significant comorbidities, short life expectancy, or history of severe hypoglycemia. More stringent (<6.5%) may be reasonable in younger patients with long disease duration if achievable without significant hypoglycemia.
Why do DKA patients have hypokalemia on treatment despite initially normal or high potassium?expand_more
Total body potassium is depleted in DKA from osmotic diuresis. However, initial serum K+ may be normal or high because acidosis drives K+ out of cells in exchange for H+. When insulin is given and pH corrects, K+ shifts back intracellularly — causing rapid, dangerous hypokalemia. This is why K+ must be >3.5 before starting insulin, and potassium must be repleted throughout DKA treatment.
What is the first-line oral medication for Type 2 diabetes?expand_more
Metformin is the first-line oral agent for Type 2 diabetes in the absence of contraindications. It reduces hepatic glucose production (inhibits gluconeogenesis via AMPK activation), is weight-neutral, has a low hypoglycemia risk, and reduces cardiovascular mortality. Contraindicated in eGFR <30 mL/min/1.73m² and held before contrast administration.
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.