How the adrenal gland is tested on Step 1
Match each zone to its hormone and regulator.
| Zone | Hormone | Main regulator |
|---|---|---|
| Zona glomerulosa | Aldosterone | Angiotensin II, potassium |
| Zona fasciculata | Cortisol | ACTH |
| Zona reticularis | Androgens (DHEA) | ACTH |
| Medulla | Epinephrine, norepinephrine | Sympathetic preganglionic fibers; cortisol induces PNMT |
Memory aid "GFR" for the zones, outside in: salt, sugar, sex.
Adrenal insufficiency
ACTH level separates primary from secondary.
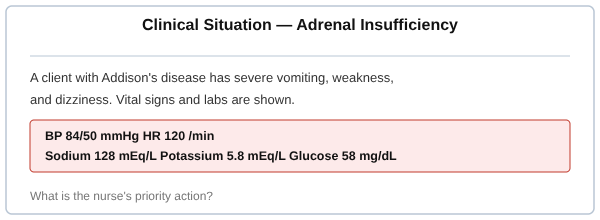
- Adrenal crisis: shock, vomiting, abdominal pain, hypoglycemia; give IV hydrocortisone and fluids immediately.
- Long-term treatment: hydrocortisone plus fludrocortisone in primary disease; increase steroid doses during illness.
Cushing syndrome
Confirm excess cortisol, then find the source.
Aldosterone, catecholamine, and enzyme disorders
Hypertension with low potassium or spells points here.
| Disorder | Findings | Treatment or clue |
|---|---|---|
| Primary hyperaldosteronism (Conn) | Hypertension, hypokalemia, metabolic alkalosis, low renin | Adenoma or bilateral hyperplasia; spironolactone or surgery |
| Secondary hyperaldosteronism | High renin (renal artery stenosis, heart failure, cirrhosis) | Treat the cause |
| Pheochromocytoma | Episodic headache, sweating, palpitations, hypertension; high metanephrines | α blocker (phenoxybenzamine) before β blocker, then surgery; MEN2, VHL, NF1 |
| 21-Hydroxylase deficiency | Salt wasting, hypotension, hyperkalemia; virilization; ↑ 17-OH progesterone | Glucocorticoid and mineralocorticoid replacement |
| 11β-Hydroxylase deficiency | Hypertension (from 11-deoxycorticosterone), low renin, virilization | Glucocorticoids |
| 17α-Hydroxylase deficiency | Hypertension, hypokalemia, no sex hormones | Ambiguous genitalia in XY; no puberty in XX |
Neuroblastoma, the most common adrenal medulla tumor in children, raises urine homovanillic and vanillylmandelic acid.
Worked example
Use ACTH and dexamethasone results.
functions Worked example — localizing Cushing syndrome
A patient with central obesity, striae, and high late-night salivary cortisol has an elevated ACTH. A high-dose dexamethasone test suppresses cortisol. Where is the lesion?
- High cortisol with high ACTH means an ACTH-dependent cause (pituitary or ectopic).
- Pituitary adenoma cells still respond to strong negative feedback.
- Suppression with high-dose dexamethasone therefore points to the pituitary.
- Ectopic ACTH tumors usually do not suppress.
Answer. Pituitary ACTH-secreting adenoma (Cushing disease); obtain pituitary MRI.