Acetaminophen Overdose: Pathophysiology, Nomogram, and N-Acetylcysteine Protocol
Acetaminophen overdose is the most common cause of acute liver failure in the United States. It is entirely treatable if identified early — NAC is nearly 100% effective when given within 8 hours. After 24 hours, the window of easy rescue closes and liver transplant may be the only option.
edit_note
Progress Note Editorial
Evidence-based · For exam prep, not medical advice
update Updated October 2026
Date of last content change
Built by surgery and anesthesiology residents·Written for USMLE Step 1
check_circleRumack-Matthew nomogram: plot level at ≥4h post-ingestion; above treatment line → give NAC
check_circleNAC near-100% effective within 8h of ingestion; still beneficial in established liver failure
check_circleRisk factors for toxicity at lower doses: chronic alcohol, fasting, INH/rifampin (CYP2E1 inducers)
Pathophysiology: NAPQI Toxicity
Normal metabolism: ~90% of acetaminophen conjugated by glucuronidation and sulfation → non-toxic. ~5% metabolized by CYP2E1 → NAPQI (N-acetyl-p-benzoquinone imine) — highly reactive toxic metabolite. NAPQI is normally conjugated by glutathione → harmless. Overdose: glutathione stores depleted → NAPQI accumulates → covalent binding to hepatocyte proteins → centrilobular necrosis (zone 3 of liver, highest CYP2E1 activity). Risk factors for increased toxicity at lower doses: chronic alcohol use (induces CYP2E1 + depletes glutathione), fasting/malnutrition (depletes glutathione), CYP2E1-inducing drugs (isoniazid, rifampin).
Clinical Stages
Stage 1 (0–24h): nausea, vomiting, malaise — minimal or no symptoms; hepatotoxicity not yet apparent. Stage 2 (24–72h): RUQ pain + elevated AST/ALT (can exceed 10,000 IU/L) + INR rising; clinical improvement of initial GI symptoms may mislead. Stage 3 (72–96h): peak hepatotoxicity — AST/ALT peak, INR >2, bilirubin rising, possible fulminant hepatic failure (encephalopathy, coagulopathy, jaundice, renal failure from hepatorenal syndrome). Stage 4 (4–14 days): recovery or death. AST/ALT very high but ASPARTATE-rich hepatocyte necrosis hallmark — AST often > ALT (unlike viral hepatitis). Renal failure: acute tubular necrosis from NAPQI direct toxicity to proximal tubules.
Rumack-Matthew Nomogram and NAC Protocol
Rumack-Matthew nomogram: plot serum acetaminophen level (drawn at ≥4h post-ingestion) against time post-ingestion on a semi-log plot. Treatment line: if level plots above the treatment line (150 mcg/mL at 4h → 37.5 mcg/mL at 12h) → treat with NAC. Below treatment line: no treatment needed. NAC (N-acetylcysteine): mechanism — replenishes glutathione stores + directly detoxifies NAPQI. Oral NAC (preferred): 140 mg/kg loading dose, then 70 mg/kg q4h × 17 doses. IV NAC (use for vomiting, pregnancy, or hepatic failure): 150 mg/kg IV over 1h, then 50 mg/kg over 4h, then 100 mg/kg over 16h. Efficacy: near-complete protection if given within 8h; still beneficial if given later (reduces mortality in established liver failure). NAC for unknown ingestion time or delayed presentation: treat empirically if level detectable.
Try it now
2 real questions on Acetaminophen Overdose
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
12
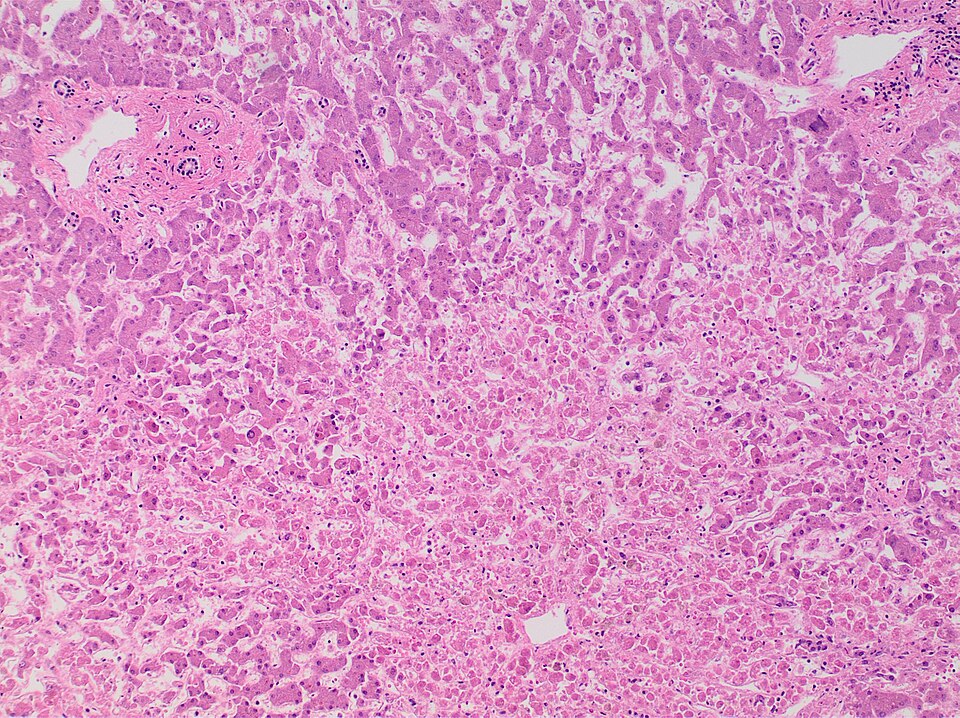
A 22-year-old woman is brought to the emergency department 36 hours after an intentional acetaminophen overdose. She now has scleral icterus, right upper quadrant tenderness, markedly elevated aminotransferases, and a prolonged INR. Liver biopsy, photomicrograph shown below, shows necrosis concentrated around the central veins with relative sparing of the periportal region. Which of the following mechanisms best explains this pattern of hepatocyte injury?
Case contributed by Dr. Linda Ferrell, UCSF Department of Pathology., Public domain, via Wikimedia Commons
Answer: E. Acetaminophen-induced hepatotoxicity results from saturation of the normal sulfation and glucuronidation conjugation pathways, shunting excess drug through cytochrome P450 2E1, which is most highly expressed in centrilobular (zone 3) hepatocytes. This generates high local concentrations of the reactive metabolite NAPQI, which depletes glutathione stores and covalently binds cellular macromolecules once glutathione is exhausted, producing the classic centrilobular necrosis pattern and explaining the delayed transaminase elevation seen 24-72 hours after overdose. Because CYP2E1 expression is concentrated in zone 3 rather than the periportal zone 1, and because the pathophysiology is metabolic rather than immune-mediated or related to chronic alcoholic change, the injury pattern is centrilobular rather than periportal or diffuse.
Source: Larson, A. M. (2007). Acetaminophen hepatotoxicity. Clinics in Liver Disease, 11(3).
A liver biopsy from a patient taking acetaminophen in overdose shows centrilobular necrosis. Which mechanism is primarily responsible for this injury?
Mikael Häggström, M.D., CC0, via Wikimedia Commons.
Answer: C. Acetaminophen overdose leads to accumulation of the toxic metabolite NAPQI, which causes hepatocellular injury. Normally, NAPQI is detoxified by glutathione, but overdose depletes glutathione stores. This results in centrilobular necrosis, where CYP450 activity is highest. Immune-mediated injury and viral effects are not responsible in this case. Thus, toxic metabolite accumulation is the key mechanism.
Source: Lee, W. M. (2017). Acetaminophen (APAP) hepatotoxicity—Isn't it time for APAP to go away? Journal of Hepatology.
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
Why should acetaminophen level be drawn at ≥4 hours post-ingestion?expand_more
Acetaminophen continues to be absorbed for up to 4 hours after oral ingestion (peak absorption ~30–90 min under normal circumstances, but may be delayed by food, enteric coating, or coingestants like opioids that slow gastric emptying). A level drawn before 4 hours may be falsely low and would be plotted at an inaccurate position on the nomogram. A level drawn at ≥4 hours reflects true peak absorption and gives a reliable toxicity prediction. If the patient presents before 4 hours, supportive care is given while awaiting the 4-hour level.
What is the King's College Criteria in acetaminophen-induced liver failure?expand_more
King's College Criteria identify patients with acetaminophen-induced acute liver failure who are unlikely to survive without liver transplantation: pH <7.3 after fluid resuscitation, OR all three of: (1) INR >6.5, (2) creatinine >3.4 mg/dL, and (3) grade III/IV hepatic encephalopathy. Meeting these criteria = immediate transplant evaluation. The ALFSG prognostic index and MELD score are also used. NAC should be continued even in patients meeting transplant criteria — it may improve outcomes while awaiting transplant.
Free weekly high-yield email
One high-yield concept + one question, every week
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Practice makes permanent
Lock this into long-term memory
Progress Note's adaptive engine spaces your reviews automatically — so this stays with you through boards and onto the wards.