Liver Function Tests Explained: Interpreting LFTs for USMLE and NCLEX
LFTs are one of the most ordered lab panels in medicine — and one of the most misinterpreted. The key is recognizing patterns, not isolated values. A systematic approach to LFTs unlocks a differential diagnosis in seconds.
Hepatocellular injury: AST and ALT elevated (aminotransferases leak from damaged hepatocytes). Typically ALT > AST (ALT is more liver-specific). Marked elevation (>10× normal — 'acute hepatitis range'): viral hepatitis (HAV, HBV, HCV), ischemic hepatitis ('shock liver' — AST/ALT >1000 IU/L, rapidly improves if perfusion restored), acetaminophen toxicity (AST/ALT often >3000-10,000), autoimmune hepatitis. Moderate elevation (3-10× normal): NASH, alcoholic hepatitis, drug-induced liver injury (DILI), Wilson's disease. AST:ALT ratio >2:1 (especially >3:1): strongly suggests alcoholic liver disease ('De Ritis ratio'). Alcoholic hepatitis: AST usually <300-400 IU/L despite severe disease; ALT characteristically lower than AST. Mnemonic: 'AST = Alcohol, Scotch & Tequila (> ALT).'
Cholestatic Pattern
Cholestatic (obstructive) injury: Alkaline phosphatase (ALP) and GGT predominantly elevated, with lesser aminotransferase elevation. ALP elevation sources: liver (bile duct disease), bone (Paget's, metastases, fractures), placenta, intestine. Distinguish hepatic vs bone ALP: GGT is liver-specific — if GGT elevated + ALP elevated → hepatic source; if GGT normal + ALP elevated → bone source. Causes of cholestatic pattern: (1) Intrahepatic cholestasis — primary biliary cholangitis (PBC), primary sclerosing cholangitis (PSC), drug-induced (estrogen, anabolic steroids, chlorpromazine), cholestasis of pregnancy, viral hepatitis with cholestatic variant. (2) Extrahepatic obstruction — choledocholithiasis, cholangiocarcinoma, pancreatic head cancer (Courvoisier's law: palpable non-tender GB + painless jaundice = malignant obstruction), pancreatic head mass, bile duct stricture.
Bilirubin Patterns
Bilirubin metabolism: unconjugated (indirect) bilirubin → liver conjugation (glucuronic acid) → conjugated (direct) bilirubin → secreted into bile. Total bilirubin = direct + indirect. Elevated indirect bilirubin (unconjugated hyperbilirubinemia): hemolysis (increased RBC breakdown → more unconjugated bilirubin produced faster than liver conjugates), ineffective erythropoiesis, Gilbert's syndrome. Gilbert's syndrome: most common hereditary hyperbilirubinemia; mild unconjugated hyperbilirubinemia with stress/fasting/illness; benign; no treatment needed; UGT1A1 promoter mutation. Elevated direct bilirubin (conjugated): hepatocellular disease (conjugated but cannot be secreted), intrahepatic cholestasis, extrahepatic obstruction, Dubin-Johnson syndrome (AR, benign, black liver pigment), Rotor syndrome.
Synthetic Function Markers
LFTs include markers of hepatic SYNTHETIC function (reflect true liver function): Prothrombin time (PT/INR): liver produces factors II, VII, IX, X (vitamin K-dependent) + V, fibrinogen. PT elevation = hepatic failure or vitamin K deficiency. Factor VII has shortest half-life → PT first to rise in acute liver failure. Albumin: made exclusively by hepatocytes; long half-life (20 days) → better marker of chronic hepatic function (cirrhosis) than acute injury. Low albumin: chronic liver disease, malnutrition, nephrotic syndrome (urinary losses), protein-losing enteropathy. MELD score: Model for End-stage Liver Disease = creatinine + bilirubin + INR → used for liver transplant waitlist prioritization.
3 real questions on Liver Function Tests Explained
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
123
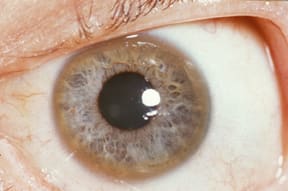
A 16-year-old presents with dysarthria, tremor, and personality change. Slit-lamp examination, image shown below, reveals golden-brown rings at the corneal limbus. Serum ceruloplasmin is low and 24-hour urinary copper is elevated. Liver biopsy shows hepatocyte copper accumulation with steatosis and Mallory-Denk bodies, and genetic testing confirms an ATP7B mutation. The hepatocellular and neurological injury in this patient result most directly from which of the following mechanisms?
Herbert L. Fred, MD, Hendrik A. van Dijk, CC BY 3.0 <https://creativecommons.org/licenses/by/3.0>, via Wikimedia Commons
Answer: A. Wilson disease results from mutations in ATP7B, a copper-transporting ATPase required for biliary copper excretion and incorporation of copper into ceruloplasmin. Loss of this transport function causes progressive accumulation of free, unbound copper within hepatocytes, where it catalyzes Fenton-type reactions generating hydroxyl radicals that damage hepatocellular membranes; once copper spills into the circulation, it similarly damages basal ganglia neurons and the cornea, producing Kayser-Fleischer rings. This is fundamentally a defect in biliary excretion rather than excessive intestinal absorption, and Wilson disease is not mediated by autoantibodies, defective cytochrome c oxidase incorporation, or hepcidin-mediated iron sequestration, distinguishing it from unrelated autoimmune or iron-storage liver diseases.
Source: Ala, A., et al. (2007). Wilson's disease. The Lancet, 369(9559).
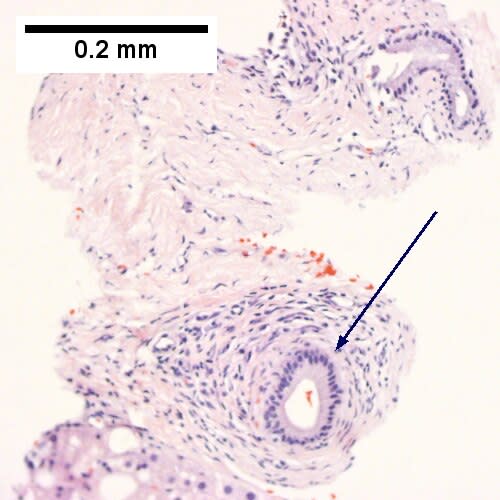
A 52-year-old woman with primary sclerosing cholangitis undergoes liver biopsy during workup for elevated alkaline phosphatase and bilirubin. The biopsy image below demonstrates a characteristic histologic finding around medium-sized bile ducts. Which of the following correctly describes the histopathologic pattern shown and the mechanism driving it?
TexasPathologistMSW, CC BY-SA 4.0 <https://creativecommons.org/licenses/by-sa/4.0>, via Wikimedia Commons
Answer: D. Primary sclerosing cholangitis (PSC) is characterized histologically by concentric periductal fibrosis producing an 'onion-skin' appearance around medium and large bile ducts, ultimately leading to ductal obliteration and loss, cholestasis, and secondary biliary cirrhosis. The fibrosis is driven by persistent biliary epithelial injury that activates portal and periductal hepatic stellate cells/myofibroblasts via TGF-β and other profibrogenic mediators. PSC is strongly associated with inflammatory bowel disease (particularly ulcerative colitis) and carries an elevated risk of cholangiocarcinoma. Option A describes primary biliary cholangitis (PBC), which features florid duct lesions with granulomatous inflammation. Option C describes autoimmune hepatitis, characterized by interface hepatitis and plasma cell infiltration. Option B describes passive congestion (e.g., Budd-Chiari or right heart failure). Option E describes NASH-related fibrosis, which is centrilobular-to-portal in distribution.
Source: Karlsen, T. H., et al. (2017). Primary sclerosing cholangitis — a comprehensive review. Journal of Hepatology, 67(6), 1298–1323.
A 22-year-old woman is brought to the emergency department 36 hours after an intentional acetaminophen overdose. She now has scleral icterus, right upper quadrant tenderness, markedly elevated aminotransferases, and a prolonged INR. Liver biopsy, photomicrograph shown below, shows necrosis concentrated around the central veins with relative sparing of the periportal region. Which of the following mechanisms best explains this pattern of hepatocyte injury?
Case contributed by Dr. Linda Ferrell, UCSF Department of Pathology., Public domain, via Wikimedia Commons
Answer: E. Acetaminophen-induced hepatotoxicity results from saturation of the normal sulfation and glucuronidation conjugation pathways, shunting excess drug through cytochrome P450 2E1, which is most highly expressed in centrilobular (zone 3) hepatocytes. This generates high local concentrations of the reactive metabolite NAPQI, which depletes glutathione stores and covalently binds cellular macromolecules once glutathione is exhausted, producing the classic centrilobular necrosis pattern and explaining the delayed transaminase elevation seen 24-72 hours after overdose. Because CYP2E1 expression is concentrated in zone 3 rather than the periportal zone 1, and because the pathophysiology is metabolic rather than immune-mediated or related to chronic alcoholic change, the injury pattern is centrilobular rather than periportal or diffuse.
Source: Larson, A. M. (2007). Acetaminophen hepatotoxicity. Clinics in Liver Disease, 11(3).
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.