How PUD is tested on Step 1
Vignettes give epigastric pain related to meals, an NSAID or H. pylori clue, or a complication such as bleeding or perforation.
Helicobacter pylori
The microbe behind most ulcers and two gastric cancers.
- Microbiology: curved, flagellated, gram-negative rod; urease converts urea to ammonia, buffering acid around the organism.
- Diseases: chronic antral gastritis, duodenal and gastric ulcers, gastric adenocarcinoma (intestinal type), and MALT lymphoma.
- Testing: urea breath test or stool antigen (both show active infection); biopsy at endoscopy. Serology cannot confirm eradication.
- Treatment: bismuth quadruple therapy (PPI, bismuth, metronidazole, tetracycline) or a clarithromycin-based triple regimen (PPI, clarithromycin, amoxicillin) where resistance is low; confirm eradication afterward.
| Gastritis | Location | Cause and consequences |
|---|---|---|
| Type A (autoimmune) | Body and fundus | Antibodies to parietal cells and intrinsic factor → achlorhydria, pernicious anemia, ↑ gastrin; risk of carcinoid and adenocarcinoma |
| Type B (H. pylori) | Antrum first | Most common; ulcers, adenocarcinoma, MALT lymphoma |
| Acute erosive | Variable | NSAIDs, alcohol, burns, shock, uremia |
Memory aid: type A = Autoimmune and Anemia; type B = Bacteria.
Complications
Location predicts the complication.
Gastrinoma and ulcer drugs
Know when ulcers are not ordinary.
- Zollinger-Ellison syndrome: gastrin-secreting tumor (duodenum or pancreas, in the "gastrinoma triangle"); refractory or multiple ulcers, jejunal ulcers, diarrhea (acid inactivates pancreatic enzymes). Elevated fasting gastrin with low gastric pH; secretin stimulation paradoxically increases gastrin. About one-quarter are part of MEN1.
- Misoprostol: PGE₁ analog that restores mucosal protection in NSAID users; causes diarrhea and is contraindicated in pregnancy (uterine contractions).
- Bismuth: coats ulcers and is antibacterial against H. pylori; can blacken the stool and tongue.
- PPIs and H₂ blockers: heal ulcers by suppressing acid; PPIs are more potent.
Worked example
Match the bleed to the artery.
functions Worked example — sudden hematemesis
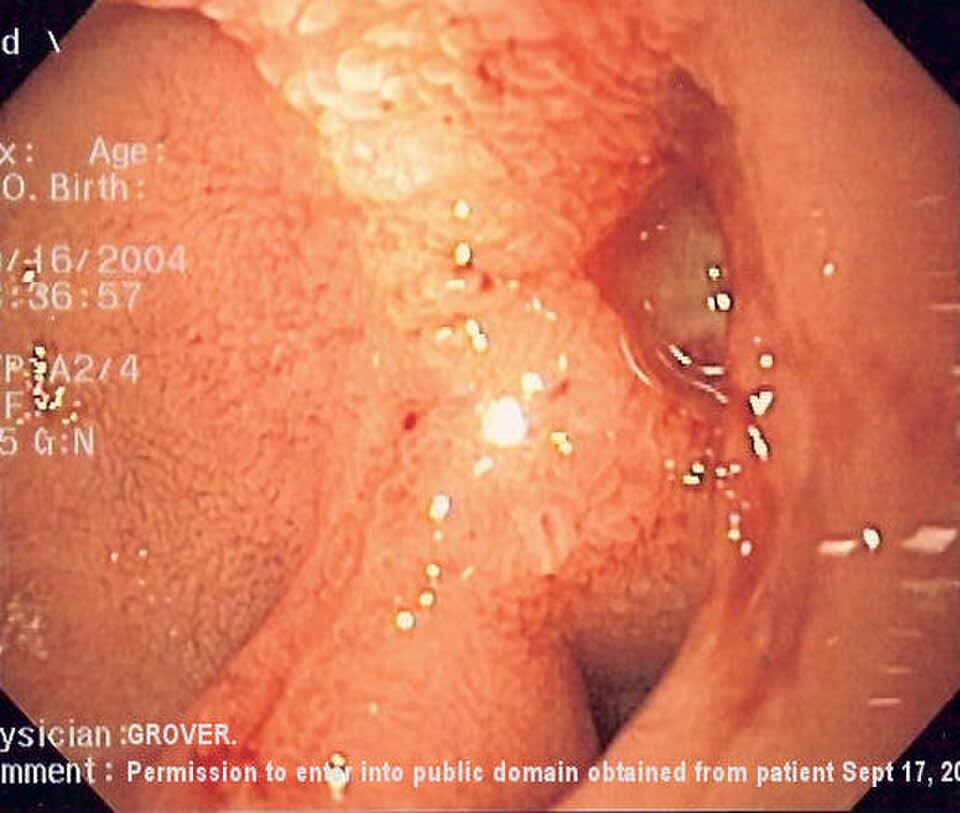
A 50-year-old with months of epigastric pain that improves after eating now vomits blood and becomes hypotensive. Endoscopy shows an ulcer on the posterior wall of the duodenal bulb with a visible vessel. Which artery is bleeding, and which organism is likely responsible?
- Pain relieved by food suggests a duodenal ulcer.
- The gastroduodenal artery runs behind the first part of the duodenum.
- A posterior duodenal ulcer can erode into it, causing major hemorrhage.
- Duodenal ulcers are most strongly associated with H. pylori.
Answer. Gastroduodenal artery bleeding from a posterior duodenal ulcer, most likely caused by H. pylori.