Anemia is a reduction in red-cell mass — most practically, a low hemoglobin or hematocrit. It looks like a huge differential, but on USMLE Step 1 it collapses into a clean algorithm anchored on one number: the mean corpuscular volume (MCV). This guide builds that approach step by step — classify by cell size, then use iron studies, the reticulocyte count, and the peripheral blood smear to reach the specific diagnosis.
Evidence-based · For exam prep, not medical advice
update Updated October 2026
Date of last content change
Built by surgery and anesthesiology residents
Written for USMLE Step 1 · Free to read
bolt The 60-second version
Anemia is a reduction in red-cell mass — most practically, a low hemoglobin or hematocrit. It looks like a huge differential, but on USMLE Step 1 it collapses into a clean algorithm anchored on one number: the mean corpuscular volume (MCV).
check_circleStart every anemia with the MCV: microcytic (<80), normocytic (80–100), or macrocytic (>100 fL).
check_circleMicrocytic causes: iron deficiency, thalassemia, anemia of chronic disease, and sideroblastic anemia.
check_circleFerritin reflects body iron stores and is the key discriminator — it is low only in true iron deficiency.
check_circleIn normocytic anemia, the reticulocyte count separates increased loss/destruction (high) from decreased production (low).
check_circleMacrocytic anemia is megaloblastic (B12 or folate deficiency, with hypersegmented neutrophils) or non-megaloblastic (liver disease, alcohol).
check_circleThe peripheral smear is diagnostic shorthand: target cells, schistocytes, sickle cells, spherocytes, and hypersegmented neutrophils each point to a cause.
target What you'll be able to do · aligned to USMLE Step 1 · Hematology
DXClassify anemia by MCV into microcytic, normocytic, and macrocytic categories with their major causes.
DXInterpret iron studies (ferritin, TIBC, serum iron, transferrin saturation) to separate iron deficiency, chronic disease, and thalassemia.
DXUse the reticulocyte count to distinguish decreased production from increased destruction/loss in normocytic anemia.
DXRecognize classic peripheral-smear morphology and the anemias it signals.
How anemia is tested on Step 1
Step 1 anemia questions give a hemoglobin plus an MCV, a set of iron studies, a reticulocyte count, or a smear description, and ask for the diagnosis or the mechanism. The winning strategy is always the same: classify by MCV first, then bring in the second-line test the vignette hands you. That structure turns a scary differential into a two-step read. It also keeps you from being misled by the presenting story — fatigue, pallor, and shortness of breath are common to every anemia, so the numbers, not the symptoms, drive the diagnosis. Work the labs in the same order every time and the answer usually falls out before you have finished reading the options.
workspace_premium The through-line
MCV first, always. Cell size narrows the differential before you touch any other number.
Classify by MCV
The mean corpuscular volume — average red-cell size — is the master branch point. Small cells, normal cells, and large cells each carry a distinct differential.
The MCV algorithm. Microcytic, normocytic, and macrocytic anemias each have a short list of causes; MCV chooses the branch, and a second test confirms the diagnosis.
MCV
Category
Major causes
<80 fL
Microcytic
Iron deficiency, thalassemia, chronic disease, sideroblastic
Anemia of chronic disease is usually normocytic but can become microcytic — a classic overlap Step 1 exploits.
MCV works because it reports the average size of the red cells, and size tracks the underlying defect. Microcytosis means the cells are underfilled — most often because there is not enough hemoglobin, whether from too little iron (iron deficiency), too little globin (thalassemia), or iron that is present but locked away (chronic disease). Macrocytosis means the cells are too big, classically because impaired DNA synthesis lets the cytoplasm mature while the nucleus lags, as happens when B12 or folate is deficient. A companion value, the red-cell distribution width (RDW), measures how uniform the cells are: it rises early in iron deficiency, where new cells are progressively smaller, but stays normal in thalassemia, where all the cells are uniformly small — a useful tiebreaker Step 1 sometimes provides.
Microcytic anemia and iron studies
For small cells, iron studies separate the top causes. The single most useful value is ferritin, which mirrors total body iron stores.
Iron study patterns. Iron deficiency lowers ferritin and raises TIBC (the body makes more transferrin to scavenge iron); anemia of chronic disease traps iron in stores, raising ferritin while lowering TIBC; thalassemia leaves iron studies normal.
The logic is worth internalizing rather than memorizing. Ferritin is the storage form of iron, so it falls only when stores are truly depleted — true iron deficiency. Transferrin (measured as TIBC) is the transport protein; the body upregulates it when iron is scarce, so TIBC rises in iron deficiency and falls in chronic disease, where iron is sequestered by hepcidin rather than absent. Thalassemia, a defect in globin-chain synthesis rather than iron supply, produces microcytosis with normal iron studies and often a disproportionately high red-cell count — a favorite way to distinguish it from iron deficiency.
Normocytic anemia and reticulocytes
When cell size is normal, the reticulocyte count is the next branch: it tells you whether the marrow is responding.
Reticulocyte count
Meaning
Examples
High
Marrow responding to loss/destruction
Hemolysis, acute hemorrhage
Low
Inadequate production
Aplastic anemia, chronic disease, early iron deficiency
A high reticulocyte count in a normocytic anemia points toward hemolysis or blood loss, not a production problem.
Reticulocytes are newly released, not-yet-mature red cells, so their number is a direct readout of marrow effort. A brisk reticulocytosis says the marrow is healthy and is replacing cells that are being lost or destroyed faster than normal — hemolysis or recent bleeding. A low or inappropriately normal count in the face of anemia says the marrow is failing to keep up, as in aplastic anemia, marrow infiltration, or the blunted production of chronic disease. When the vignette points to hemolysis, look for its supporting markers: a high lactate dehydrogenase and indirect bilirubin from red-cell breakdown, and a low haptoglobin because it binds and clears free hemoglobin. Whether the destruction is happening inside vessels or in the spleen further narrows the cause.
Read the smear
The peripheral smear is diagnostic shorthand — a single morphology often names the disease.
Each of these shapes encodes a mechanism. Schistocytes are fragmented cells sheared as they pass through fibrin strands or damaged vessels, so they signal a microangiopathic hemolytic anemia and demand a search for its cause. Spherocytes have lost the biconcave membrane that gives normal cells their central pallor, either from an inherited membrane-protein defect or from antibody-coated cells being partially eaten in the spleen, so their presence points to hereditary spherocytosis or autoimmune hemolysis and prompts a Coombs test. Target cells have too much membrane for their contents, which happens in liver disease and thalassemia. Learning the shape-to-mechanism link, rather than a flat list, lets you reason through unfamiliar smears on exam day.
error B12 vs folate
Both cause a megaloblastic, hypersegmented picture, but only B12 deficiency also causes neurologic disease (subacute combined degeneration) via impaired myelin synthesis. When the labs overlap, an elevated methylmalonic acid is specific for B12 deficiency; it is normal in isolated folate deficiency. Giving folate alone to a B12-deficient patient can correct the anemia while the neurologic damage silently progresses.
functions Worked example — read the iron studies
A menstruating woman has hemoglobin 9.5 g/dL, MCV 74 fL, ferritin low, TIBC high, and transferrin saturation low. What is the diagnosis?
MCV 74 is microcytic → iron deficiency, thalassemia, chronic disease, or sideroblastic.
Low ferritin means depleted iron stores — specific for true iron deficiency.
High TIBC and low transferrin saturation fit iron deficiency (not chronic disease, where TIBC is low).
Answer. Iron-deficiency anemia — the combination of low ferritin, high TIBC, and low transferrin saturation is diagnostic, and menstrual blood loss is the likely source.
How to study it — and the traps to avoid
Anemia rewards a rigid two-step approach plus the pattern recognition of iron studies and the smear.
Always classify by MCV before anything else.
Learn the iron-study patterns cold; ferritin is the discriminator (low only in iron deficiency).
Use reticulocytes to split normocytic anemia into production vs destruction/loss.
Memorize the smear morphologies and their one-to-one associations.
workspace_premium Integration
Macrocytic (B12) anemia links to neurologic findings, and microangiopathic hemolysis (schistocytes) connects to systemic disease processes tested elsewhere.
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
123
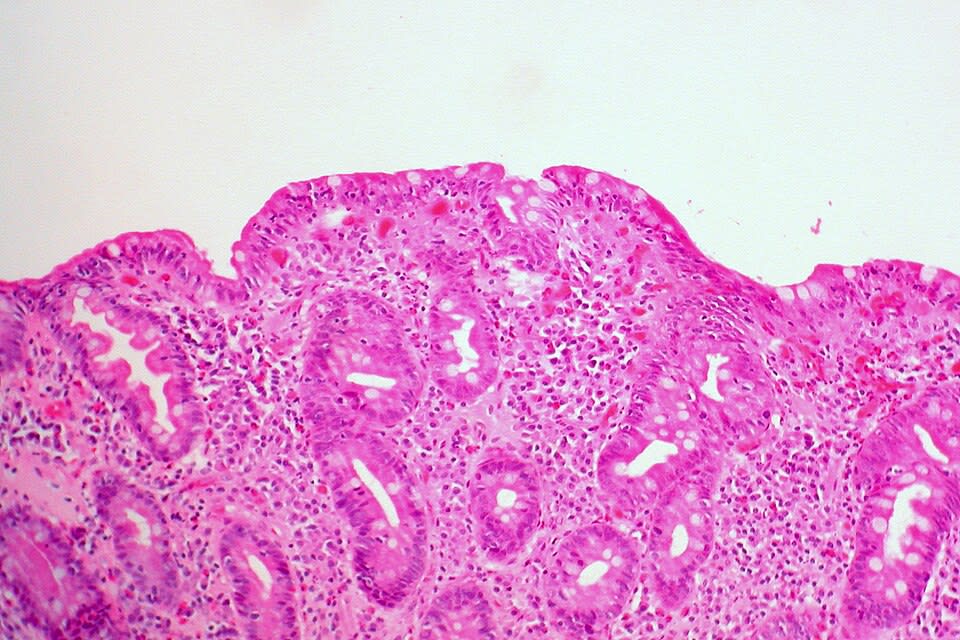
A 45-year-old woman undergoes evaluation for chronic diarrhea and weight loss. She is found to have steatorrhea, iron-deficiency anemia, and low serum folate. Duodenal biopsy reveals villous atrophy, crypt hyperplasia, and increased intraepithelial lymphocytes. Serological testing is positive for anti-tissue transglutaminase IgA antibodies. Which of the following best explains the mechanism by which fat malabsorption occurs in this condition?
Ed Uthman from Houston, TX, USA, CC BY 2.0 <https://creativecommons.org/licenses/by/2.0>, via Wikimedia Commons
Answer: B. Celiac disease is a T cell–mediated autoimmune enteropathy triggered by gluten (gliadin) in genetically susceptible individuals (HLA-DQ2/DQ8). Inflammatory destruction of the small intestinal mucosa causes villous blunting and ultimately flat villous atrophy, dramatically reducing the absorptive surface area available for nutrient uptake. Simultaneously, compensatory crypt hyperplasia repopulates the mucosa with immature enterocytes that lack mature brush border enzymes and transporters — including those required for micellar fat absorption and fatty acid esterification. The result is steatorrhea, along with deficiencies in iron, folate, calcium, and fat-soluble vitamins. Pancreatic exocrine insufficiency (option A) is a distinct entity with normal villous architecture and fecal elastase deficiency; anti-TG2 antibodies do not inhibit pancreatic lipase (option C).
Source: Green, P. H., & Cellier, C. (2007). Celiac disease. New England Journal of Medicine, 357(17), 1731–1743.
A newborn is noted to have jaundice within the first 24 hours of life. Laboratory evaluation reveals hemolytic anemia, indirect hyperbilirubinemia, and Heinz bodies on peripheral smear. The infant's red blood cells demonstrate increased sensitivity to oxidative stress. Genetic analysis confirms an X-linked recessive mutation affecting the enzyme responsible for the rate-limiting step of the pentose phosphate pathway. Which of the following substrates is most directly depleted as a result of this enzyme deficiency?
Joan-Lluis Vives-Corrons, Elena Krishnevskaya, CC BY 4.0 <https://creativecommons.org/licenses/by/4.0>, via Wikimedia Commons
Answer: D. Glucose-6-phosphate dehydrogenase (G6PD) deficiency is an X-linked recessive disorder in which the rate-limiting step of the pentose phosphate pathway (oxidative phase) is impaired, reducing production of NADPH. NADPH is required to regenerate reduced glutathione (GSH) via glutathione reductase; without sufficient GSH, oxidative species denature hemoglobin, forming Heinz bodies, and damage the erythrocyte membrane, causing intravascular hemolysis. Heinz bodies are aggregates of denatured hemoglobin visible with crystal violet staining. Option A is incorrect; ATP depletion and osmotic lysis characterize hereditary spherocytosis or pyruvate kinase deficiency. Option C is incorrect because pyruvate metabolism is not directly impaired in G6PD deficiency. Option B is incorrect; heme synthesis is not affected by G6PD. Option E is a partial truth—ribose-5-phosphate is also reduced, but this does not cause hemolytic anemia at this clinical level.
Source: Cappellini, M. D., & Fiorelli, G. (2008). Glucose-6-phosphate dehydrogenase deficiency. Lancet, 371(9606), 64–74.
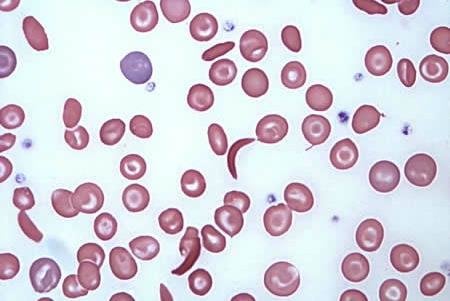
A patient has chronic hemolytic anemia with target cells and jaundice. Genetic testing reveals a mutation affecting beta-globin structure. Which condition is most likely?
Viv Caruna, CC BY 2.0 <https://creativecommons.org/licenses/by/2.0>, via Wikimedia Commons
Answer: A. Sickle cell disease is caused by a mutation in the beta-globin gene leading to hemoglobin S formation and sickling of red blood cells. This causes chronic hemolysis, splenomegaly, and vaso-occlusive crises. Hereditary spherocytosis involves membrane protein defects. Iron deficiency causes microcytosis rather than hemolysis. Autoimmune hemolytic anemia involves antibody-mediated RBC destruction.
Source: Piel, et al. (2017). Sickle cell disease. New England Journal of Medicine.
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.