Hypercalcemia (corrected serum calcium >10.5 mg/dL) is most commonly caused by primary hyperparathyroidism (outpatient) or malignancy (inpatient). The clinical presentation follows 'bones, stones, groans, and psychic moans,' and treatment severity depends on the calcium level and symptoms.
edit_note
Progress Note Editorial
Evidence-based · For exam prep, not medical advice
update Updated October 2026
Date of last content change
Built by surgery and anesthesiology residents·Written for USMLE Step 1
bolt The 60-second version
check_circlePrimary hyperparathyroidism = most common cause overall (high PTH + high Ca); malignancy = most common inpatient cause (suppressed PTH)
check_circleCHIMPANZEES mnemonic covers all causes; check PTH first to distinguish PTH-mediated from non-PTH-mediated
check_circleTreatment: IV normal saline first, then bisphosphonates (zoledronic acid) for malignancy-related; calcitonin for rapid bridge
check_circleSteroids for vitamin D-mediated hypercalcemia (sarcoid, lymphoma); parathyroidectomy for primary HPT meeting surgical criteria
Causes of Hypercalcemia: CHIMPANZEES
The CHIMPANZEES mnemonic covers all major causes: **C**alcium supplementation excess, **H**yperparathyroidism (primary — most common overall; tertiary in CKD), **I**mmobilization (increased bone resorption), **M**ilk-alkali syndrome, **P**aget disease (primarily with immobilization), **A**ddison's disease (adrenal insufficiency), **N**eoplasm/malignancy (second most common overall; most common inpatient cause — PTHrP, osteolytic mets, lymphoma via 1,25-OH-D), **Z**ollinger-Ellison (MEN1), **E**xcess vitamin D (granulomatous diseases: sarcoid, TB, histoplasma — macrophages convert 25-OH-D to active 1,25-OH-D), **E**ctopic PTH (rare), **S**arcoidosis and other granulomatous diseases. Primary hyperparathyroidism: high PTH + high calcium (50% asymptomatic, found on routine labs). Malignancy: suppressed PTH + very high calcium (PTHrP from squamous cell, renal, bladder cancers; osteolytic mets from breast, myeloma; lymphoma via calcitriol).
Clinical Features and Diagnosis
**Bones**: osteitis fibrosa cystica (primary HPT), pathologic fractures, subperiosteal bone resorption (radial aspect of middle phalanx on X-ray — classic HPT sign). **Stones**: nephrolithiasis (calcium oxalate/phosphate stones), nephrocalcinosis, nephrogenic DI, polyuria. **Groans**: nausea, vomiting, constipation, anorexia, peptic ulcers (gastrin stimulated by calcium), pancreatitis. **Psychic moans**: depression, cognitive dysfunction, lethargy, stupor, coma. **ECG**: shortened QT interval (calcium shortens phase 2 of cardiac action potential) — opposite of hypocalcemia. **Workup**: first check corrected calcium (add 0.8 mg/dL per 1 g/dL albumin below 4) or ionized calcium. Then PTH: if elevated → primary/tertiary HPT; if suppressed → malignancy workup (PTHrP, SPEP, imaging). Check PTHrP, vitamin D levels (25-OH and 1,25-OH), ACE level (sarcoid), SPEP.
Treatment by Severity
**Mild (10.5–12 mg/dL, asymptomatic)**: oral hydration, treat underlying cause. Monitor for worsening. **Moderate–severe (>12 or symptomatic)**: IV normal saline aggressive hydration (3–4 L in first few hours; furosemide only after adequate hydration to prevent pulmonary edema, NOT as first-line). **Bisphosphonates** (zoledronic acid or pamidronate): osteoclast inhibition — onset 24–48h, peak effect 2–4 days; drug of choice for malignancy-associated hypercalcemia. **Calcitonin**: fastest-acting (hours), but tachyphylaxis within 48h; useful as bridge until bisphosphonates kick in. **Corticosteroids**: for vitamin D-mediated hypercalcemia (sarcoid, lymphoma) — suppress macrophage 1α-hydroxylase. **Denosumab** (RANK-L inhibitor): useful when bisphosphonates fail. **Hemodialysis**: for severe hypercalcemia with renal failure. **Primary HPT management**: parathyroidectomy if symptomatic, Ca >1 mg/dL above normal, age <50, T-score ≤−2.5, 24h urine calcium >400 mg, or creatinine clearance <60.
Try it now
2 real questions on Hypercalcemia
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
12
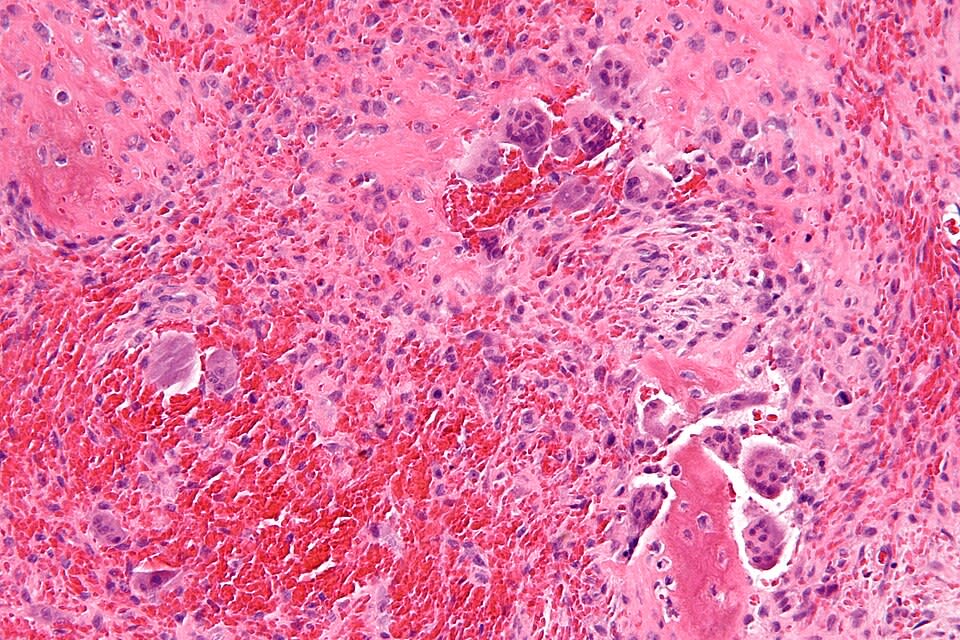
A 55-year-old woman is found to have hypercalcemia, an elevated intact parathyroid hormone level, and a low serum phosphate. Neck ultrasound identifies a single, well-circumscribed hypoechoic nodule, and pathology after excision shows a solitary parathyroid adenoma composed of sheets of chief cells with a rim of compressed normal parathyroid tissue. Several months later, she develops a painful, expansile lytic lesion of the femur; biopsy is shown below. Which mechanism most directly links her parathyroid pathology to this skeletal lesion?
Nephron, CC BY-SA 3.0 <https://creativecommons.org/licenses/by-sa/3.0>, via Wikimedia Commons
Answer: A. Chronic, unregulated PTH secretion increases osteoblast expression of RANKL, which binds RANK on osteoclast precursors to promote their differentiation and activity; the resulting excessive, localized bone resorption produces the fibrovascular, hemorrhagic, giant cell-rich brown tumor, whose color derives from hemosiderin deposition from repeated microhemorrhage. Option B is incorrect because the lesion is lytic and hemorrhagic, not a site of calcium deposition. Option C incorrectly bypasses the osteoblast-RANKL-RANK axis, since PTH receptors are expressed on osteoblasts, not directly on mature osteoclasts. Option D is incorrect because the lesion is osteolytic, reflecting net bone loss rather than new bone formation. Option E introduces an unrelated hormonal axis not implicated in this patient's presentation.
Source: Carsote, M., et al. (2024). Brown tumors: The hidden face of primary and renal hyperparathyroidism amid real-life settings. Journal of Clinical Medicine, 13(13).
From our NCLEX bank
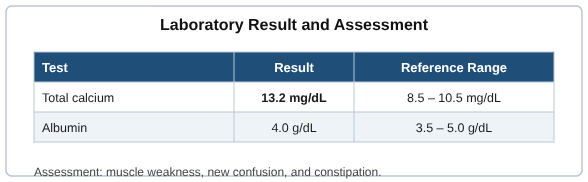
A nurse reviews the laboratory result and assessment shown. How should the nurse interpret and respond to these findings?
Answer: A. A total calcium of 13.2 mg/dL with a normal albumin is high, and with muscle weakness, confusion, and constipation it indicates hypercalcemia, so the nurse promotes hydration, monitors the cardiac rhythm, and notifies the provider (option A). The calcium is high, not low, so hypocalcemia with seizure precautions (B) is incorrect. The value is clearly abnormal, not normal (C). The problem involves calcium, not potassium, so treating for hyperkalemia (D) does not fit. Hypercalcemia can cause dysrhythmias and altered mental status, so the nurse encourages fluids to promote calcium excretion and monitors closely. Recognizing the imbalance guides safe treatment.
Source: Pagana, K. D., Pagana, T. J., & Pagana, T. N. (2022). Mosby's diagnostic and laboratory test reference (16th ed.). Elsevier.
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
How do I differentiate primary hyperparathyroidism from malignancy-related hypercalcemia?expand_more
PTH level is the key: primary HPT has elevated or inappropriately normal PTH with hypercalcemia. Malignancy suppresses PTH to near zero. Check PTHrP (elevated in humoral hypercalcemia of malignancy — squamous cell, RCC), 24h urine calcium, vitamin D levels, and SPEP. Primary HPT is usually chronic and asymptomatic; malignancy-related is acute, severe, and symptomatic.
Why should furosemide not be used first-line for hypercalcemia?expand_more
Loop diuretics can worsen hypercalcemia if the patient is volume-depleted by increasing proximal tubular calcium reabsorption. IV normal saline must be given first to ensure adequate volume status and promote urinary calcium excretion. Furosemide is only added after euvolemia is established and only if the patient is at risk for fluid overload.
Free weekly high-yield email
One high-yield concept + one question, every week
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Practice makes permanent
Lock this into long-term memory
Progress Note's adaptive engine spaces your reviews automatically — so this stays with you through boards and onto the wards.