Acute Kidney Injury Workup: Prerenal vs Intrinsic vs Postrenal
AKI complicates ~7% of hospitalizations and up to 30% of ICU admissions. The classic triad of elevated creatinine, decreased urine output (<0.5 mL/kg/hr), and fluid/electrolyte derangements requires immediate systematic classification to direct treatment.
KDIGO AKI criteria: creatinine rise ≥0.3 mg/dL within 48h, OR ≥1.5× baseline within 7 days, OR urine output <0.5 mL/kg/hr × ≥6h. Stage 1: Cr ×1.5–1.9 baseline or ↑≥0.3 within 48h. Stage 2: Cr ×2–2.9 baseline. Stage 3: Cr ×3 baseline or ≥4.0 mg/dL or RRT needed. BUN:Cr ratio: >20:1 suggests prerenal (concentrated urine, avid BUN reabsorption); <10–15:1 suggests intrinsic renal disease. Note: BUN elevation from GI bleed, corticosteroids, or high protein intake raises BUN independently of renal function — contextualize the ratio.
Prerenal AKI
Cause: reduced renal perfusion without intrinsic kidney damage. Etiologies: volume depletion (dehydration, GI losses, hemorrhage), low cardiac output (CHF, cardiogenic shock), vasodilation (sepsis, cirrhosis), renal vasoconstriction (NSAIDs block prostaglandin vasodilation; ACEi/ARBs block efferent arteriole constriction). Urine: high osmolality (>500 mOsm/kg), low urine Na (<20 mEq/L), FENa <1%. Treatment: fluid challenge — NS or LR bolus. If due to NSAIDs: stop NSAID. If hepatorenal syndrome (cirrhosis + prerenal AKI unresponsive to fluids): midodrine + octreotide + albumin, or terlipressin (if available) as bridge to liver transplant.
Intrinsic AKI
Glomerular: RBC casts (GN), proteinuria — treat underlying GN (immunosuppression for RPGN). Tubular (ATN — most common intrinsic): muddy brown casts, ischemia (sepsis, shock), nephrotoxins (aminoglycosides, contrast, cisplatin, myoglobin/rhabdomyolysis). FENa >2% (tubules cannot reabsorb Na). Treatment: remove offending agent, supportive — ATN is reversible in 1–3 weeks if cause removed. Interstitial (AIN): WBC casts + eosinophiluria, drug hypersensitivity (NSAIDs, PPIs, beta-lactams, sulfa), fever + rash + eosinophilia (triad in only 10%). Treatment: discontinue offending drug, steroids if no improvement. Vascular: TTP/HUS (schistocytes), renal artery stenosis.
Postrenal AKI and Indications for Dialysis
Postrenal: obstruction of urine flow. In hospitalized patients: foley catheter obstruction, neurogenic bladder. Outpatient causes: BPH (bilateral obstruction), bilateral ureteral stones, retroperitoneal mass, cervical cancer. Diagnosis: bladder ultrasound or catheter drainage for bladder outflow obstruction; renal ultrasound for hydronephrosis (bilateral for postrenal AKI). Treatment: relieve obstruction — catheter, stent, or percutaneous nephrostomy. Post-obstructive diuresis: watch for massive urine output and replace fluids/electrolytes. AEIOU indications for urgent dialysis: Acidosis (pH <7.1), Electrolytes (K+ >6.5 or refractory), Intoxication (methanol, ethylene glycol, lithium, salicylates), Overload (refractory pulmonary edema), Uremia (encephalopathy, pericarditis, bleeding).
Try it now
3 real questions on Acute Kidney Injury Workup
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
123
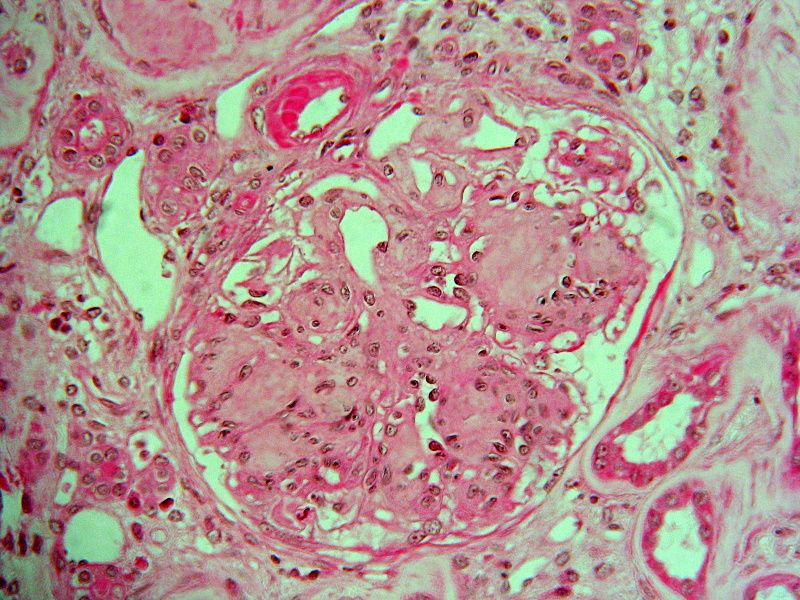
A kidney biopsy shows nodular mesangial expansion with thickened glomerular basement membranes on light microscopy. Which underlying condition is most consistent with these histologic findings?
Doc.mari, CC BY-SA 3.0 <https://creativecommons.org/licenses/by-sa/3.0>, via Wikimedia Commons
Answer: B. Diabetic nephropathy is characterized by nodular mesangial expansion (Kimmelstiel-Wilson nodules) and thickened glomerular basement membranes. Hypertensive nephrosclerosis typically shows hyaline arteriolosclerosis rather than nodules. Minimal change disease lacks significant light microscopy findings. Poststreptococcal and IgA nephropathies show immune complex deposition with hypercellularity. These nodular lesions are classic for diabetic kidney disease.
Source: Tervaert, et al. (2010). Pathologic classification of diabetic nephropathy. Journal of the American Society of Nephrology.
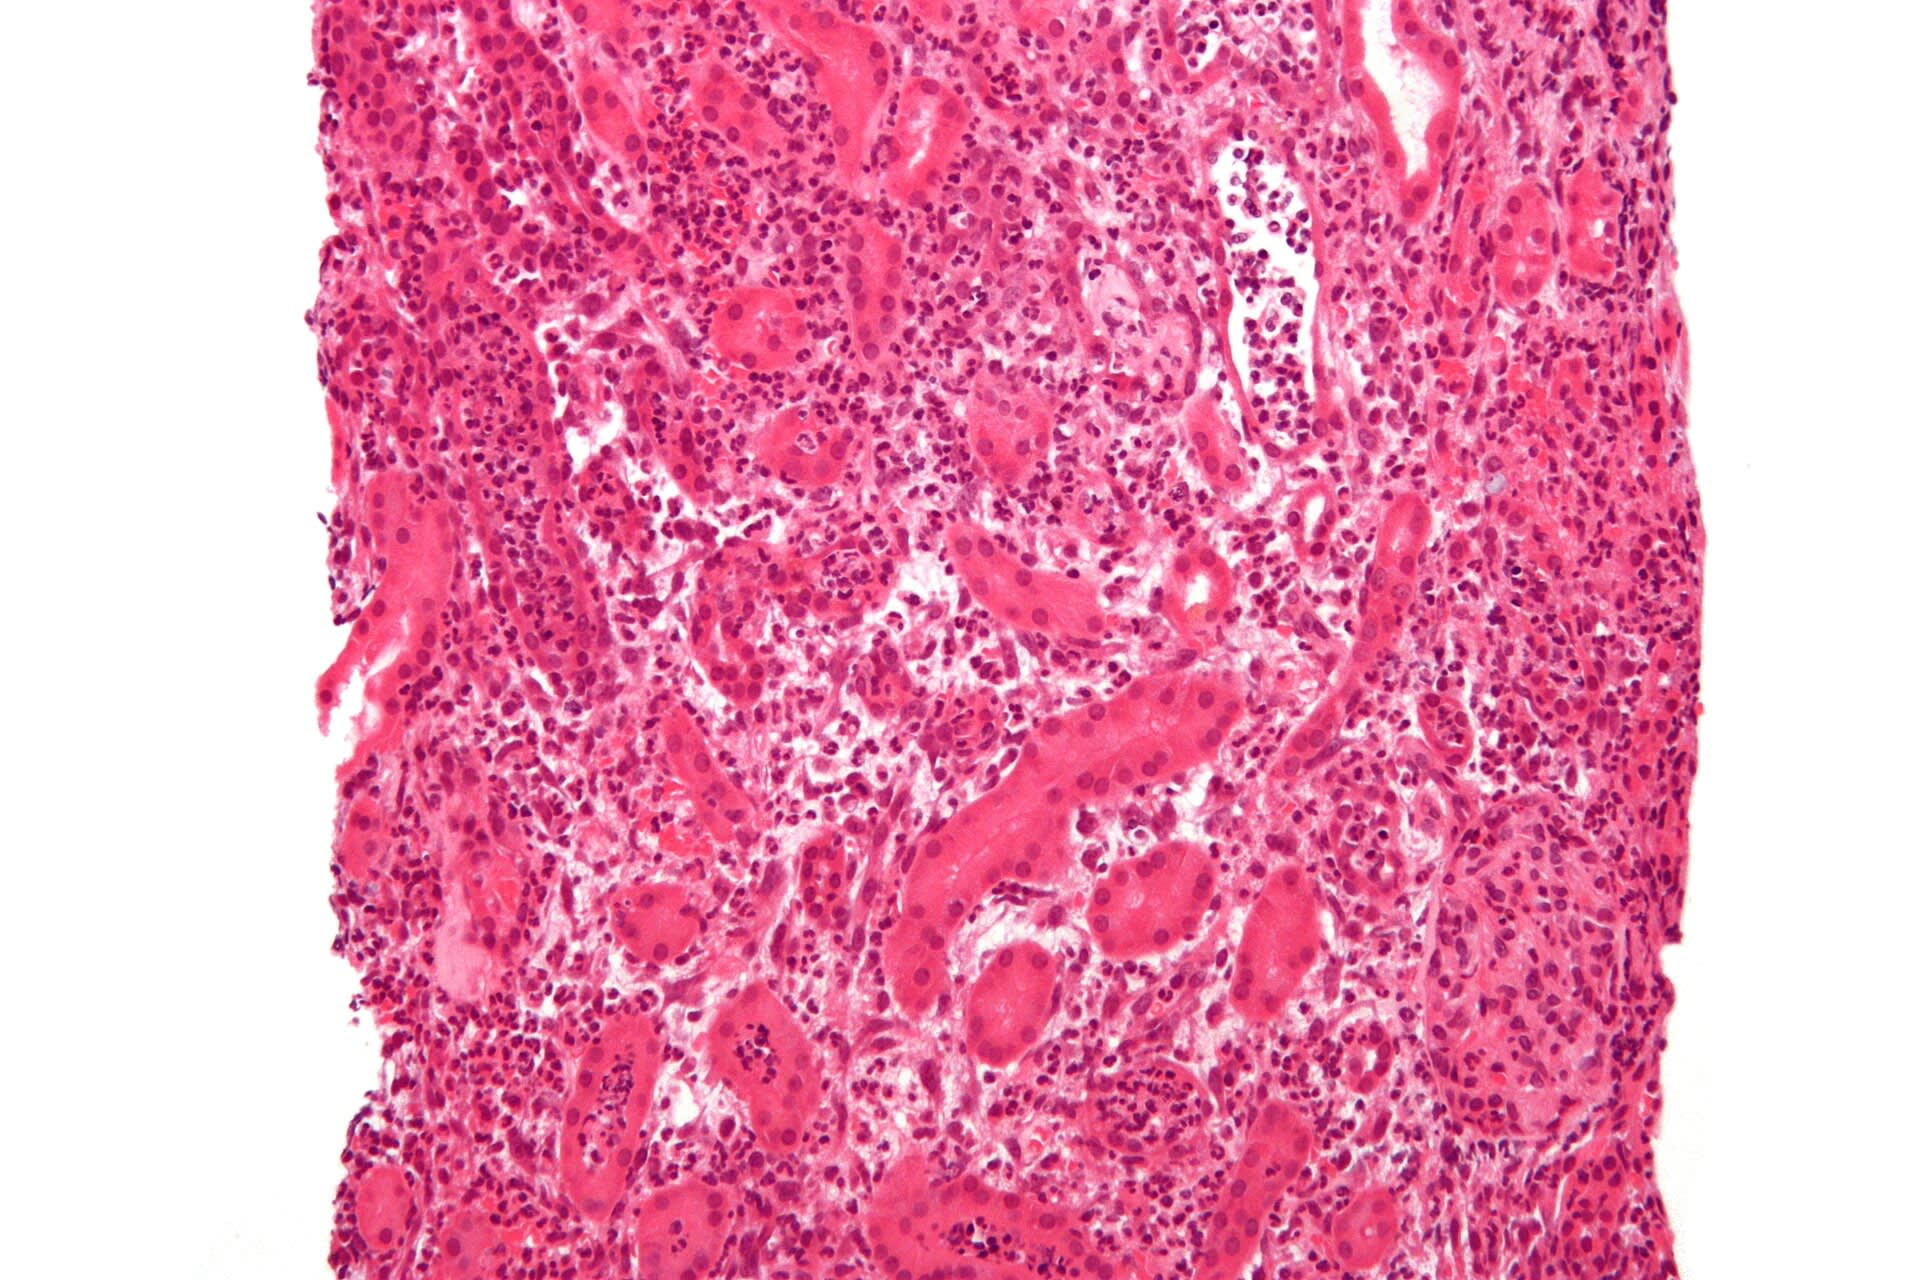
A 28-year-old woman presents with fever, flank pain, and dysuria. Urinalysis shows leukocyte esterase positivity and nitrites. Gross examination of the kidney would most likely reveal which finding?
Nephron, CC BY-SA 3.0 <https://creativecommons.org/licenses/by-sa/3.0>, via Wikimedia Commons
Answer: B. Acute pyelonephritis is a bacterial infection of the kidney, most commonly caused by ascending gram-negative organisms such as E. coli. Gross pathology typically shows patchy, yellow-white abscesses and streaking of the renal medulla due to neutrophilic infiltration along the tubules. Option A describes chronic pyelonephritis or chronic renal disease with scarring. Option C is more consistent with amyloidosis or other infiltrative diseases. Option D represents renal infarction, which lacks suppurative inflammation. Option E describes polycystic kidney disease.
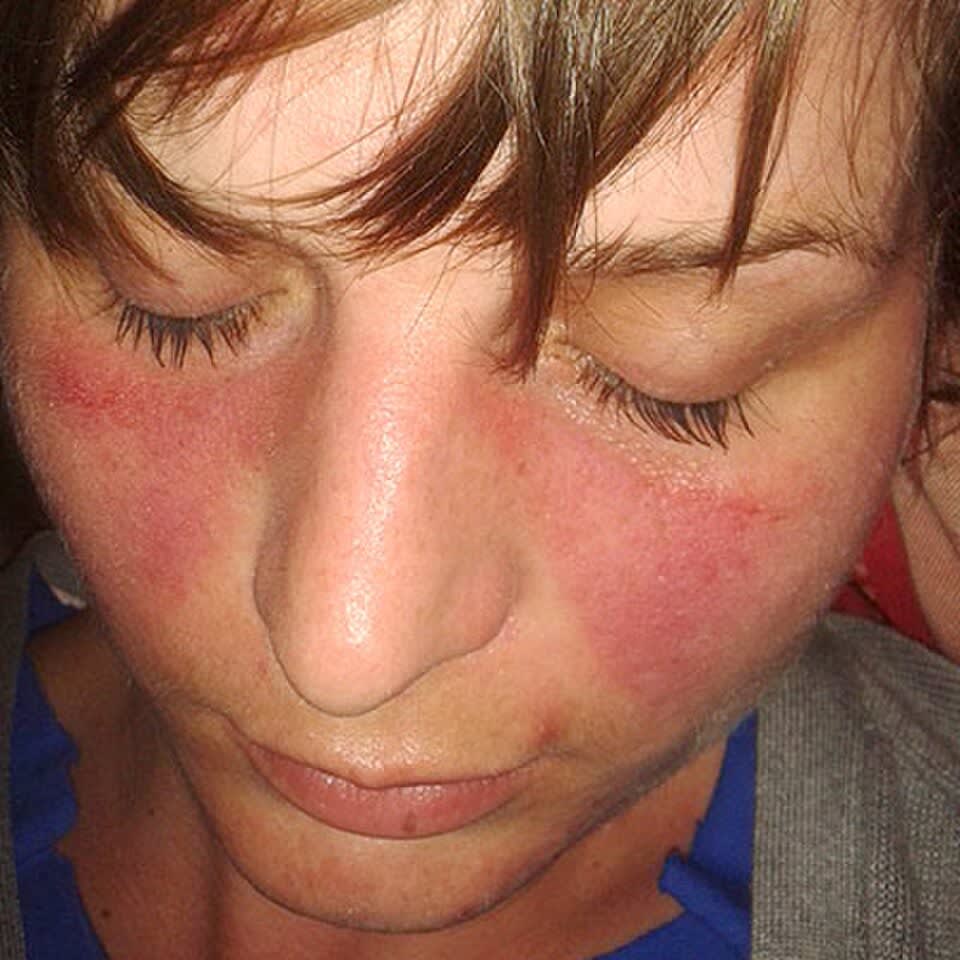
A 32-year-old woman presents with a 6-month history of joint pain, a malar rash, and fatigue. Laboratory studies reveal a positive ANA (titer 1:640, homogeneous pattern), positive anti-dsDNA antibodies, low serum C3 and C4, and proteinuria. Kidney biopsy shows mesangial and subendothelial immune complex deposits with 'full house' immunofluorescence (IgG, IgA, IgM, C3, C1q). Which of the following best explains the mechanism of complement consumption in this patient?
Doktorinternet, CC BY-SA 4.0 <https://creativecommons.org/licenses/by-sa/4.0>, via Wikimedia Commons
Answer: B. In systemic lupus erythematosus (SLE), anti-dsDNA and other autoantibodies form immune complexes with nuclear antigens released from apoptotic cells. These immune complexes deposit in the glomeruli and activate the classical complement pathway: C1q binds the Fc regions of IgG (and IgM) within the complexes, sequentially activating C1r, C1s, C4, and C2 to generate C3 convertase, driving consumption of C3 and C4. Low C3 and C4 therefore indicate active classical pathway consumption and correlate with lupus nephritis activity. 'Full house' immunofluorescence (IgG, IgA, IgM, C3, C1q) is pathognomonic for lupus nephritis. The alternative pathway (option A) consumes C3 without C4 reduction; isolated low C3 with normal C4 suggests MPGN type II or C3 glomerulopathy rather than lupus.
Source: Tsokos, G. C. (2011). Systemic lupus erythematosus. New England Journal of Medicine, 365(22), 2110–2121.
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
Why is FENa unreliable in patients on diuretics?expand_more
Fractional excretion of sodium (FENa = [UNa × PCr] / [PNa × UCr] × 100) reflects tubular sodium handling. In prerenal AKI, intact tubules avidly reabsorb Na → FENa <1%. However, diuretics (especially loop diuretics) directly force natriuresis, raising urine sodium independent of volume status — falsely elevating FENa above 1% even in true prerenal disease. Alternative: FEUrea (<35% = prerenal) is not affected by diuretics and is more reliable when diuretics have been given within the past 24 hours.
What are the indications for emergency dialysis in AKI?expand_more
The AEIOU mnemonic: Acidosis (metabolic acidosis pH <7.1 or HCO3 <8 mEq/L refractory to treatment), Electrolytes (hyperkalemia K+ >6.5 or any potassium with ECG changes unresponsive to medical therapy), Intoxication (removal of dialyzable toxins: methanol, ethylene glycol, lithium, salicylates, certain barbiturates), Overload (pulmonary edema refractory to diuretics), Uremia (encephalopathy, asterixis, uremic pericarditis with friction rub, uremic bleeding — BUN usually >100 mg/dL).
Free weekly high-yield email
One high-yield concept + one question, every week
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.