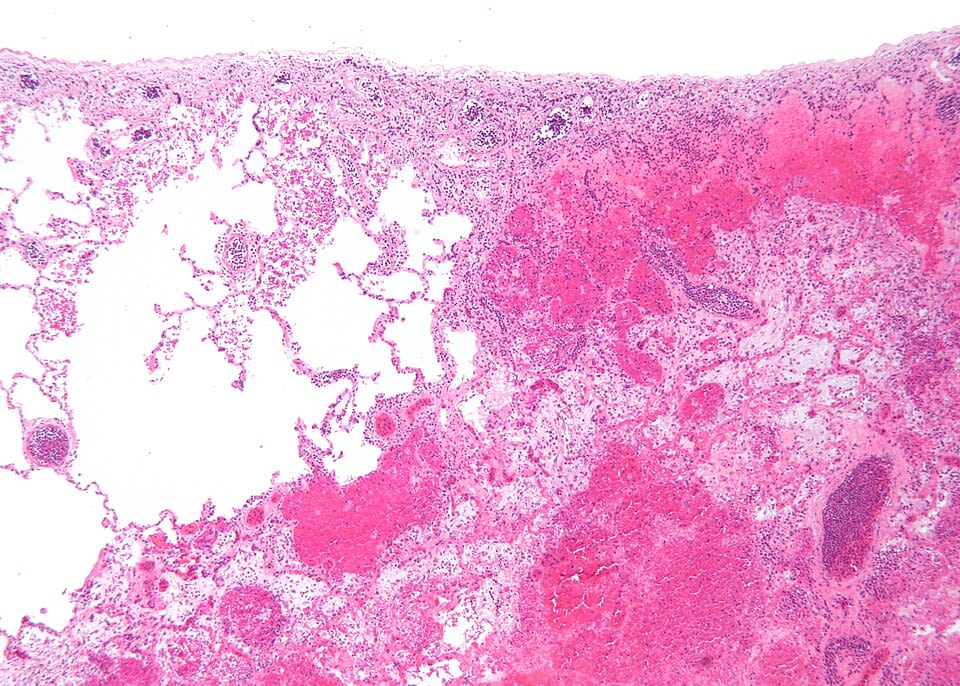
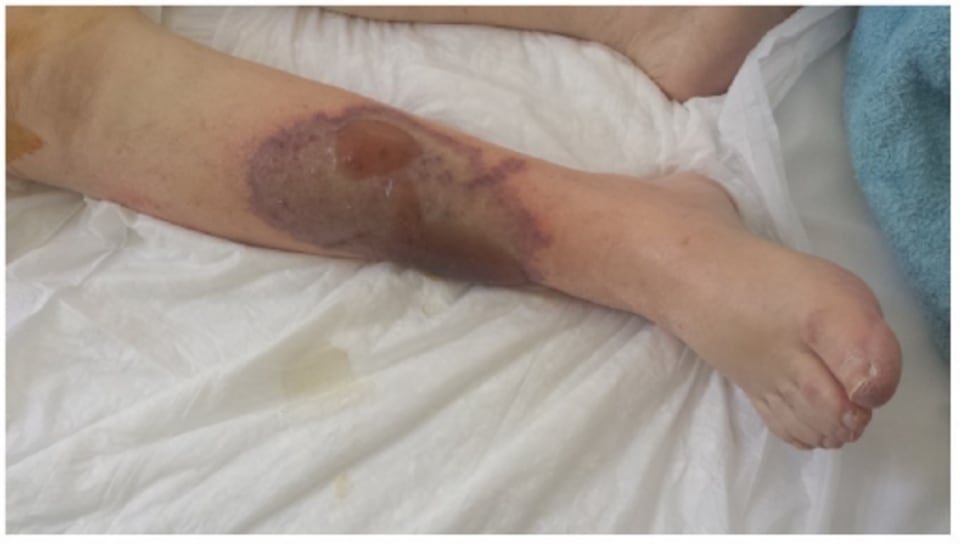
How VTE is tested on Step 1
Expect a postoperative, immobilized, pregnant, or cancer patient with sudden dyspnea, and questions about the next diagnostic step, the blood gas, or anticoagulant choice.
Use pretest probability to choose the test. A negative D-dimer rules out PE only when probability is low or intermediate; high probability goes straight to CT pulmonary angiography.
Risk factors and pathophysiology
Any factor in Virchow triad raises risk; many patients have several.
| Virchow element | Examples |
|---|---|
| Stasis | Immobilization, long flights, surgery, heart failure, atrial fibrillation |
| Endothelial injury | Trauma, surgery (especially orthopedic), central venous catheters |
| Hypercoagulability | Cancer, pregnancy and postpartum, estrogen therapy, factor V Leiden, prothrombin mutation, antiphospholipid syndrome, nephrotic syndrome |
Factor V Leiden (resistance to activated protein C) is the most common inherited thrombophilia in people of European ancestry.
Diagnosis
Clinical prediction rules guide testing.
| Finding | Typical result in PE |
|---|---|
| Arterial blood gas | Hypoxemia, hypocapnia, respiratory alkalosis, ↑ A–a gradient |
| ECG | Sinus tachycardia most common; S1Q3T3, right heart strain, new RBBB (uncommon) |
| Chest x-ray | Often normal; Hampton hump (wedge infarct), Westermark sign (oligemia) |
| Troponin, BNP | Elevated with RV strain — worse prognosis |
| Echocardiogram | RV dilation, McConnell sign |
A normal chest x-ray in a hypoxemic patient should raise suspicion for PE.
Treatment
Treatment depends on hemodynamic stability and bleeding risk.
Clinical application
The blood gas is a frequent test of PE physiology.
Five days after a total knee replacement, a 66-year-old develops sudden dyspnea and pleuritic chest pain. HR 118, RR 28, SpO₂ 89%. ABG: pH 7.49, PaCO₂ 30 mm Hg, PaO₂ 62 mm Hg on room air. Chest x-ray is clear. Explain the gas and the next step.
- Recent orthopedic surgery and immobility give high pretest probability.
- Low PaO₂ with a clear x-ray suggests V/Q mismatch from dead space.
- Hypoxemia and anxiety drive hyperventilation, lowering PaCO₂ and causing respiratory alkalosis.
- A–a gradient = (150 − 30/0.8) − 62 ≈ 50 mm Hg, clearly elevated.
Answer. Pulmonary embolism with V/Q mismatch. With high probability, go directly to CT pulmonary angiography (skip D-dimer) and start anticoagulation if no contraindication.