Penicillins and cephalosporins are β-lactam antibiotics that bind penicillin-binding proteins and block peptidoglycan cross-linking. Step 1 organizes them as a ladder of increasing gram-negative coverage, adds the drugs designed to resist β-lactamases, and tests allergy cross-reactivity and a few distinctive toxicities.
check_circleAminopenicillins (ampicillin, amoxicillin) add H. influenzae, E. coli, Listeria, Proteus, Salmonella, enterococci (HHELPSS).
check_circleAntipseudomonal piperacillin is paired with tazobactam; cephalosporins gain gram-negative coverage with each generation; ceftaroline covers MRSA.
check_circleTrue penicillin allergy has low cross-reactivity with most cephalosporins (< 2%); avoid in anaphylaxis history if side chains are similar.
target What you'll be able to do · aligned to USMLE Step 1 · Pharmacology — Antimicrobials
PHARMDescribe the mechanism of β-lactam antibiotics and the main resistance mechanisms.
PHARMMatch each penicillin class to its spectrum and classic indications.
PHARMDescribe the coverage of each cephalosporin generation and the organisms none cover.
PHARMRecognize β-lactam hypersensitivity patterns and estimate cross-reactivity.
How β-lactams are tested on Step 1
Questions ask which penicillin covers a given organism, which cephalosporin generation fits an infection, or what explains a rash, seizure, or interstitial nephritis.
workspace_premium Four bugs no cephalosporin covers
LAME: Listeria, Atypicals (Chlamydia, Mycoplasma), MRSA (except ceftaroline), and Enterococci.
Mechanism and resistance
β-lactams acylate the active site of penicillin-binding proteins, stopping the final cross-linking of peptidoglycan. Autolysins then lyse the cell.
β-lactam mechanism. MRSA resists through PBP2a (mecA); penicillin-resistant pneumococci have altered PBPs; gram-negatives make β-lactamases.
Penicillin classes
Climb the ladder: each step adds gram-negative coverage.
Penicillin ladder. Amoxicillin–clavulanate adds β-lactamase producers such as H. influenzae, Moraxella, and anaerobes.
Drug
Classic use
Notable toxicity
Benzathine penicillin G
Syphilis; rheumatic fever prophylaxis
Jarisch-Herxheimer reaction in syphilis
Nafcillin, oxacillin
MSSA bacteremia, endocarditis
Interstitial nephritis (classically methicillin)
Amoxicillin
Otitis media, sinusitis, H. pylori, Lyme
Rash in EBV mononucleosis
Ampicillin
Listeria meningitis, enterococcal infections
Pseudomembranous colitis
Piperacillin-tazobactam
Hospital-acquired and Pseudomonas infections
Seizures at high dose
Nafcillin is cleared by the liver, so it needs no renal dose adjustment.
Cephalosporin generations
Moving up the generations generally adds gram-negative coverage and CNS penetration.
Generation
Examples
Coverage
Uses
1st
Cefazolin, cephalexin
Gram-positive cocci + PEcK (Proteus, E. coli, Klebsiella)
Surgical prophylaxis, skin infections, MSSA
2nd
Cefoxitin, cefuroxime
+ HEN (H. influenzae, Enterobacter, Neisseria); cefoxitin covers anaerobes
Ceftriaxone can cause biliary sludge and is avoided in neonates (displaces bilirubin; precipitates with calcium).
Allergy and adverse effects
Hypersensitivity is the most common serious β-lactam reaction.
Allergy and cross-reactivity. Aztreonam is the safe β-lactam choice in severe penicillin allergy.
functions Worked example — the mono rash
A 17-year-old with sore throat, posterior cervical lymphadenopathy, and fatigue is given amoxicillin for presumed strep pharyngitis. Two days later a diffuse maculopapular rash appears. Is this a penicillin allergy?
Posterior lymphadenopathy, fatigue, and pharyngitis in a teenager suggest EBV infectious mononucleosis.
Aminopenicillins cause a nonallergic rash in most patients with active EBV infection.
It does not predict future true penicillin allergy.
Answer. Probably not a true allergy — it is the classic amoxicillin rash in EBV mononucleosis. Confirm with a heterophile test; amoxicillin was not indicated.
3 real questions on Penicillins and Cephalosporins
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
123
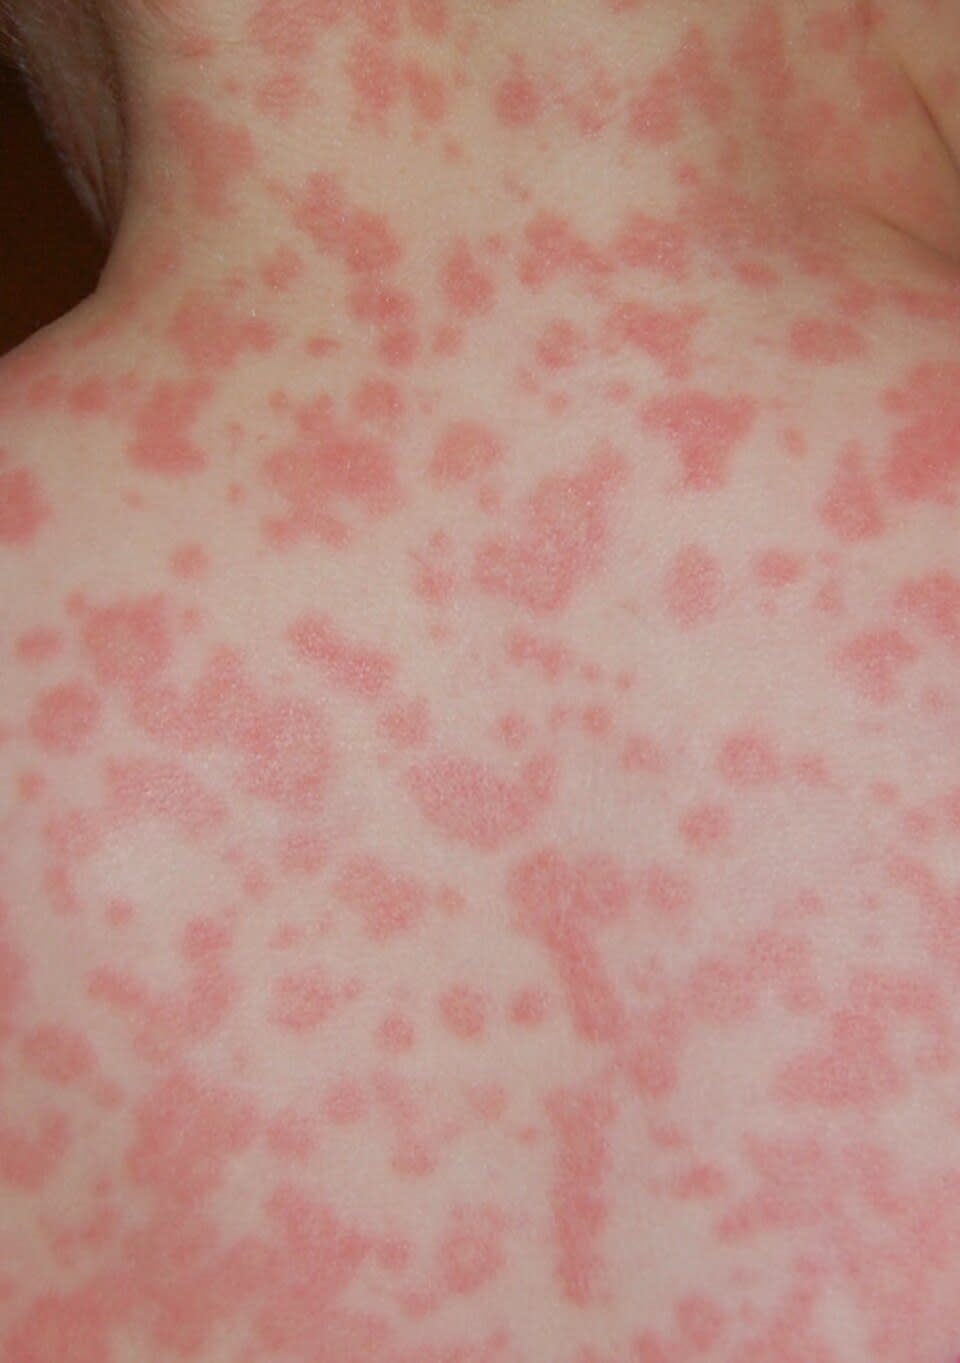
A 19-year-old college student presents with a 1-week history of fever, sore throat, cervical lymphadenopathy, and fatigue. On examination he has tonsillar exudates and splenomegaly. Monospot test is positive. Three days into his illness, he is prescribed amoxicillin by an urgent care provider for presumed streptococcal pharyngitis, after which he develops a diffuse maculopapular rash. Which of the following best describes the mechanism of the rash in this patient?
Skoch3, CC BY-SA 4.0 <https://creativecommons.org/licenses/by-sa/4.0>, via Wikimedia Commons
Answer: D. The maculopapular rash that occurs in a significant proportion of EBV-infected patients given aminopenicillins (amoxicillin, ampicillin) is a T cell–mediated non-allergic drug hypersensitivity reaction that is specific to the context of active EBV infection, not a true IgE-mediated penicillin allergy. The proposed mechanism involves altered immune reactivity during EBV-driven lymphoproliferation, producing drug-reactive T cell clones. This reaction does not predict future allergic reactions to penicillins and patients should not be labeled as penicillin-allergic on this basis. IgE-mediated allergy (option A) would typically present with urticaria and onset within minutes to an hour. Cross-reactivity between viral antigens and drug epitopes (option E) has not been substantiated as the mechanism.
Source: Chovel-Sella, et al. (2013). Incidence of rash after amoxicillin treatment in children with infectious mononucleosis. Pediatrics, 131(5), e1424–e1427.
From our NCLEX bank
A nurse is preparing to give a prescribed antibiotic and notes the client's record lists an allergy to penicillin. The prescribed drug is a cephalosporin. Which action by the nurse is most appropriate?
Answer: D. The nurse clarifies with the provider and asks what the client's penicillin reaction actually was, because that detail determines whether a cephalosporin is safe (option D). Giving the drug because it is a different class (A) ignores the possibility of cross-reactivity and the fact that the reaction history matters. Giving it and watching closely (B) accepts a preventable risk of anaphylaxis rather than resolving it first. Omitting the dose without follow-up (C) leaves the infection untreated and the question unanswered. The nurse documents the specific reaction rather than only the word allergy, since intolerance and true allergy require different decisions.
As a nurse prepares to give a newly ordered antibiotic, the client reports a penicillin allergy that is not listed in the record. Which action by the nurse is most appropriate?
Answer: A. A client-reported allergy is taken seriously, so the nurse holds the drug, verifies the allergy and the type of reaction, updates the record, and clarifies the order with the provider (option A). Giving the antibiotic because the allergy is undocumented (B) ignores a potentially life-threatening risk. Giving a test dose to see what happens (C) deliberately exposes the client to possible anaphylaxis. Adding an antihistamine to prevent a reaction (D) does not make an inappropriate antibiotic safe. Verifying and acting on the reported allergy protects the client from a serious reaction. The nurse documents the allergy and reaction and ensures the record and the plan are updated.
The penicillinase-resistant penicillins: nafcillin, oxacillin, and dicloxacillin. Cefazolin is an alternative.
What does amoxicillin cover that penicillin does not?expand_more
Some gram-negative organisms — H. influenzae, E. coli, Proteus, Salmonella, and Shigella — plus Listeria and enterococci.
Which organisms do cephalosporins not cover?expand_more
Listeria, atypical organisms (Chlamydia, Mycoplasma), MRSA (except ceftaroline), and enterococci — remembered as LAME.
Can patients with penicillin allergy take cephalosporins?expand_more
Usually yes. Cross-reactivity is under 2% and depends on side-chain similarity. Patients with prior anaphylaxis should avoid cephalosporins with similar side chains or undergo testing.
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.