Meningitis is inflammation of the meninges surrounding the brain and spinal cord, most dangerously from bacterial infection. On USMLE Step 1 it is a compact, high-yield topic that rewards three skills: reading the cerebrospinal fluid (CSF) profile, matching the likely organism to the patient’s age, and choosing empiric therapy. This guide connects the lumbar puncture, the CSF numbers, and the age-based bugs into one approach.
Evidence-based · For exam prep, not medical advice
update Updated October 2026
Date of last content change
Built by surgery and anesthesiology residents
Written for USMLE Step 1 · Free to read
bolt The 60-second version
Meningitis is inflammation of the meninges surrounding the brain and spinal cord, most dangerously from bacterial infection. On USMLE Step 1 it is a compact, high-yield topic that rewards three skills: reading the cerebrospinal fluid (CSF) profile, matching the likely organism to the patient’s age, and choosing empiric therapy.
check_circleThe classic triad is fever, headache, and nuchal rigidity — though not all three are always present.
check_circleCSF analysis is the key test: bacterial meningitis shows neutrophils, low glucose, and high protein; viral shows lymphocytes with normal glucose.
check_circleFungal and tuberculous meningitis show lymphocytes with low glucose and high protein — a viral-looking cell type with a bacterial-looking glucose.
check_circleAge drives the organism: neonates (GBS, E. coli, Listeria); children/adults (S. pneumoniae, N. meningitidis); elderly/immunocompromised (add Listeria).
check_circleThe lumbar puncture is done at L3–L4 or L4–L5 — below the spinal cord’s termination (~L1–L2) — so the cord is not injured.
check_circleDo not delay antibiotics for imaging or LP in suspected bacterial meningitis; empiric therapy is time-critical.
target What you'll be able to do · aligned to USMLE Step 1 · Infectious Disease / Nervous System
DXInterpret the CSF profile (cell type, glucose, protein) to distinguish bacterial from viral and fungal/tuberculous meningitis.
PATHMatch the most likely causative organism to patient age and immune status.
DXDescribe the lumbar puncture — where it is performed and why it is safe.
RXSelect age-appropriate empiric antibiotic therapy, including when to add Listeria coverage.
How meningitis is tested on Step 1
Step 1 meningitis questions almost always hand you a lumbar puncture result and ask you to classify the cause, or give an age and ask for the organism or the empiric antibiotic. A few test the anatomy of the LP itself or the urgency of treatment. The unifying skill is reading the CSF numbers against the clinical context, and doing it quickly, because in a truly bacterial case every hour of delayed antibiotics worsens the outcome.
workspace_premium The through-line
Three inputs decide almost every question: the CSF profile, the patient’s age, and the timing of treatment.
The lumbar puncture
The diagnosis rests on sampling CSF by lumbar puncture. Understanding where and why the needle goes explains a favorite anatomy question.
The lumbar puncture. The needle enters at the L3–L4 or L4–L5 interspace, below where the spinal cord ends (~L1–L2), passing among the nerve roots of the cauda equina without injuring the cord.
The spinal cord tapers to its end, the conus medullaris, at roughly the L1–L2 level in adults, but the subarachnoid space and its CSF continue well below that as the lumbar cistern. That anatomy is what makes the lumbar puncture safe: entering at L3–L4 or L4–L5 reaches CSF while the needle floats among the mobile nerve roots of the cauda equina rather than piercing the cord. A useful surface landmark is the top of the iliac crests, which lie roughly at the L4 spinous process. One important caveat Step 1 tests: in a patient with signs of markedly raised intracranial pressure or a focal mass, a lumbar puncture can precipitate brain herniation, so imaging precedes the tap in that setting — but antibiotics must not wait for either.
Reading the CSF
The CSF profile is the heart of the diagnosis. Three numbers — the predominant white cell, the glucose, and the protein — sort the major causes.
CSF profiles. Bacterial meningitis produces neutrophils with low glucose and high protein; viral produces lymphocytes with normal glucose; fungal/TB produces lymphocytes with low glucose and high protein.
Cause
Cells
Glucose
Protein
Opening pressure
Bacterial
Neutrophils (PMNs)
↓↓ Low
↑ High
High
Viral
Lymphocytes
Normal
Normal/mildly ↑
Normal/high
Fungal / TB
Lymphocytes
↓ Low
↑ High
High
The discriminator is glucose: bacteria and fungi/TB consume it (low), whereas viruses do not (normal).
Read the three numbers as a small logic puzzle. The predominant white cell reflects the immune response: pyogenic bacteria recruit neutrophils, while the slower, cell-mediated response to viruses, fungi, and tuberculosis brings lymphocytes. The CSF glucose reflects consumption: organisms that metabolize glucose — bacteria, fungi, and mycobacteria — drive it down, whereas viruses, which replicate inside host cells without consuming free glucose, leave it normal. Protein rises whenever the blood–CSF barrier is inflamed and leaky, so it is high in most infectious meningitides and highest in bacterial and tuberculous disease. Because CSF glucose depends on the serum level, it is compared as a ratio; a CSF-to-serum glucose ratio below about two-thirds is the meaningful threshold, which is why the vignette gives you both values.
Age-based organisms
Once the CSF says “bacterial,” the patient’s age predicts the most likely organism — and therefore the empiric antibiotics.
Bugs by age. Neonates: group B Streptococcus, E. coli, and Listeria; children and adults: S. pneumoniae and N. meningitidis; elderly and immunocompromised: S. pneumoniae plus Listeria.
Age group
Key organisms
Empiric coverage
Neonate
GBS, E. coli, Listeria
Ampicillin + cefotaxime (or gentamicin)
Child / adult
S. pneumoniae, N. meningitidis
Vancomycin + ceftriaxone
>50 / immunocompromised
Above + Listeria
Vancomycin + ceftriaxone + ampicillin
Ampicillin is added at the extremes of age (and in immunocompromise) specifically to cover Listeria, which cephalosporins miss.
The age map reflects exposure and immunity. Neonates acquire group B Streptococcus, E. coli, and Listeria from the maternal genital and gastrointestinal flora around birth, which is why their empiric regimen looks different from everyone else’s. Beyond the newborn period, the encapsulated organisms Streptococcus pneumoniae and Neisseria meningitidis dominate, the latter especially in crowded settings such as college dormitories and military barracks. At the other extreme, waning immunity in older adults and the immunocompromised reopens the door to Listeria, so ampicillin returns to the regimen. Vaccination has reshaped this landscape: routine Haemophilus influenzae type b and pneumococcal conjugate vaccines have sharply reduced those causes in immunized children, a public-health point Step 1 sometimes rewards.
Putting it together
With the CSF and the age in hand, meningitis becomes a rapid, structured decision.
functions Worked example — read the CSF
A 19-year-old college student has fever, headache, and neck stiffness. LP shows 3,000 neutrophils, glucose 25 mg/dL (serum 90), and elevated protein. What is the diagnosis and empiric therapy?
Neutrophils with low glucose and high protein → bacterial meningitis.
A young adult, especially in a dormitory, raises concern for N. meningitidis and S. pneumoniae.
Empiric therapy covers both with vancomycin plus a third-generation cephalosporin.
Answer. Bacterial meningitis (likely N. meningitidis or S. pneumoniae). Start vancomycin + ceftriaxone empirically, without delay; add dexamethasone for suspected pneumococcal disease.
error Common trap
Fungal/TB meningitis has lymphocytes (like viral) but low glucose (like bacterial). The low glucose is the tell that this is not a benign viral meningitis.
How to study it — and the traps to avoid
Meningitis rewards memorizing the CSF grid and the age-organism map, then moving fast.
Memorize the CSF table cold — cells, glucose, and protein for bacterial, viral, and fungal/TB.
Learn the age-based organisms and the Listeria rule (extremes of age → add ampicillin).
Know the LP level (L3–L4/L4–L5) and when imaging must precede it.
Never delay empiric antibiotics for imaging or the tap in suspected bacterial meningitis.
Straight from the Progress Note question bank, each with a cited explanation. No account needed.
123
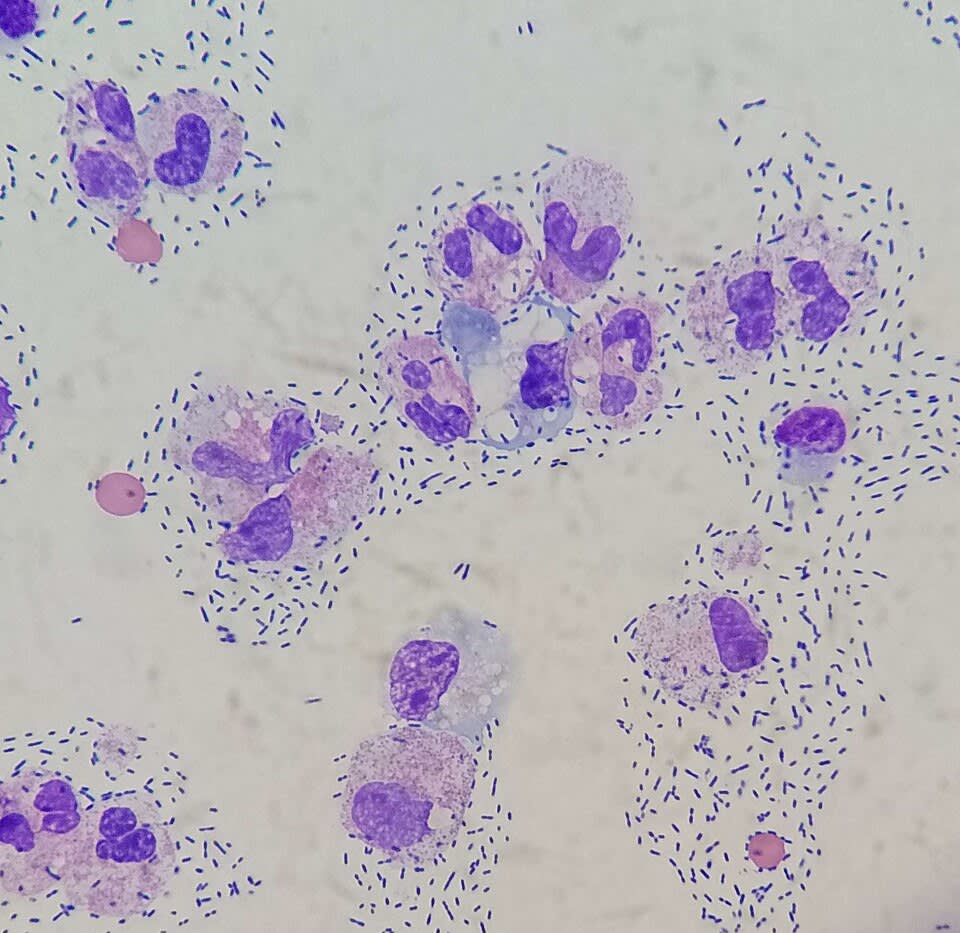
A 28-year-old man with fever, severe headache, photophobia, and neck stiffness is hospitalized with suspected bacterial meningitis. Lumbar puncture reveals CSF with protein 250 mg/dL, glucose 30 mg/dL (serum glucose 110 mg/dL), and WBC 1200/µL with 85% neutrophils. CSF differential is shown below. Dura mater biopsy shows an acute suppurative inflammatory exudate with dense neutrophilic infiltrate, fibrin deposition, and bacterial cocci. Which of the following best explains the pathophysiology of bacterial meningitis and the relationship between bacterial virulence factors, blood-brain barrier breakdown, and the characteristic CSF findings in this patient?
Spicy, CC BY 4.0 <https://creativecommons.org/licenses/by/4.0>, via Wikimedia Commons
Answer: B. Bacterial meningitis begins with hematogenous seeding of meningeal vasculature; bacterial cell wall components (peptidoglycan, lipopolysaccharide, lipoteichoic acid) are recognized by pattern recognition receptors (TLRs) on meningeal macrophages and microglia, triggering release of pro-inflammatory cytokines (TNF-alpha, IL-1, IL-6, IL-8). These cytokines increase vascular permeability by disrupting tight junction proteins (claudins, occludin, ZO-1) and inducing expression of adhesion molecules; consequently, the blood-brain barrier becomes permeable, allowing leukocyte extravasation and protein leak into the CSF. Hypoglycorrhachia (low CSF glucose despite normal serum glucose) results from impaired glucose transport into CSF via GLUT1 transporters on choroid plexus epithelium due to inflammation and acidosis, combined with increased glucose consumption by infiltrating neutrophils. The characteristic CSF profile shows pleocytosis dominated by neutrophils, elevated protein (from barrier disruption), and reduced glucose-to-serum ratio (<0.4). Options A, D, and E invoke incorrect or incomplete mechanisms; option C underestimates the role of intact immunity in preventing meningitis.
Source: van de Beek, D., et al. (2021). Community-acquired bacterial meningitis. The Lancet, 398(10306).
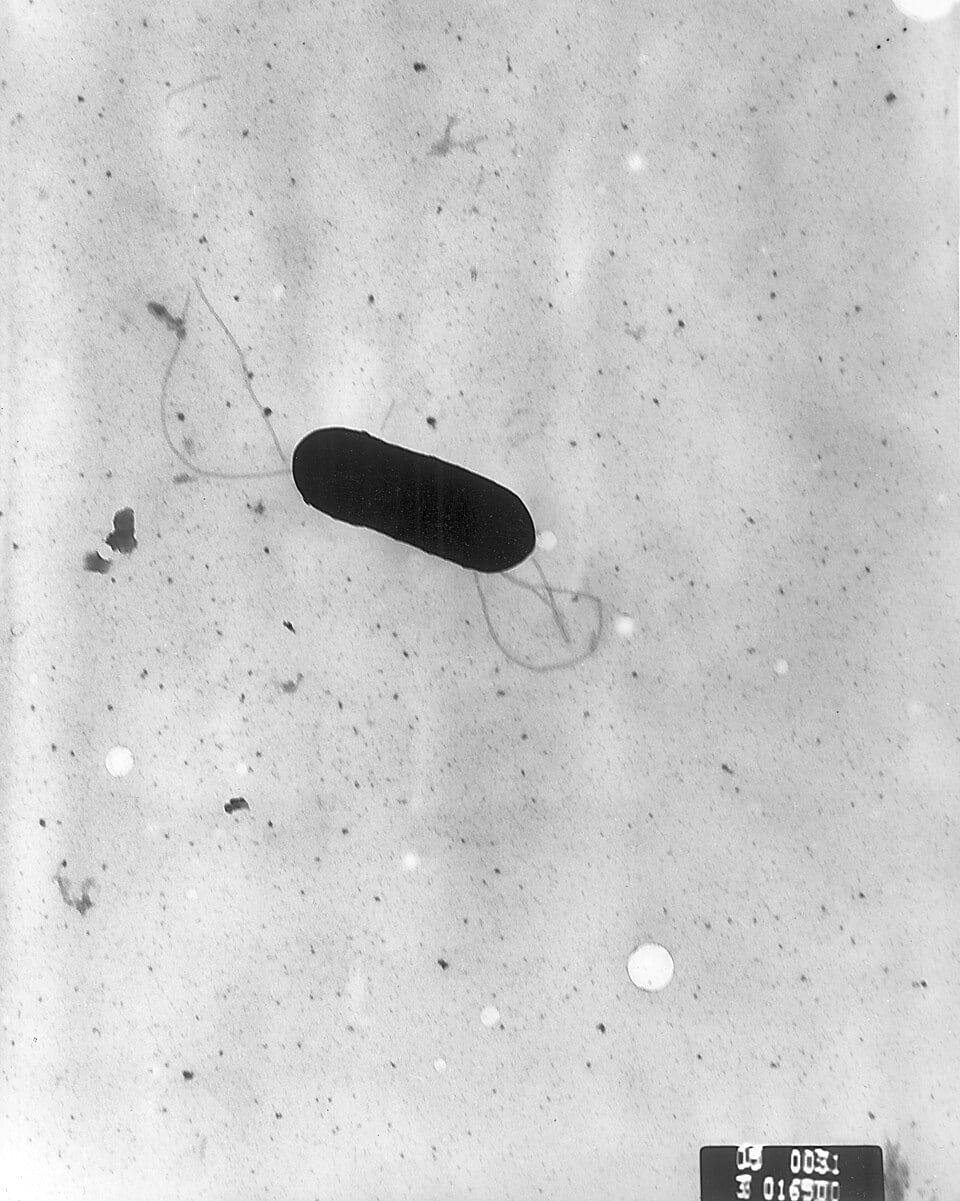
A patient presents with meningitis after eating unpasteurized cheese. Which organism is most likely responsible?
Elizabeth White, Public domain, via Wikimedia Commons
Answer: A. Listeria monocytogenes is associated with unpasteurized dairy and causes meningitis in neonates, elderly, and immunocompromised patients. It is a gram-positive intracellular rod. Neisseria meningitidis causes meningitis in adolescents. Streptococcus pneumoniae is the most common cause of adult meningitis. Haemophilus influenzae is less common due to vaccination.
Source: Radoshevich, et al. (2018). Listeria monocytogenes: towards a complete picture of its physiology and pathogenesis. Nature Reviews Microbiology.
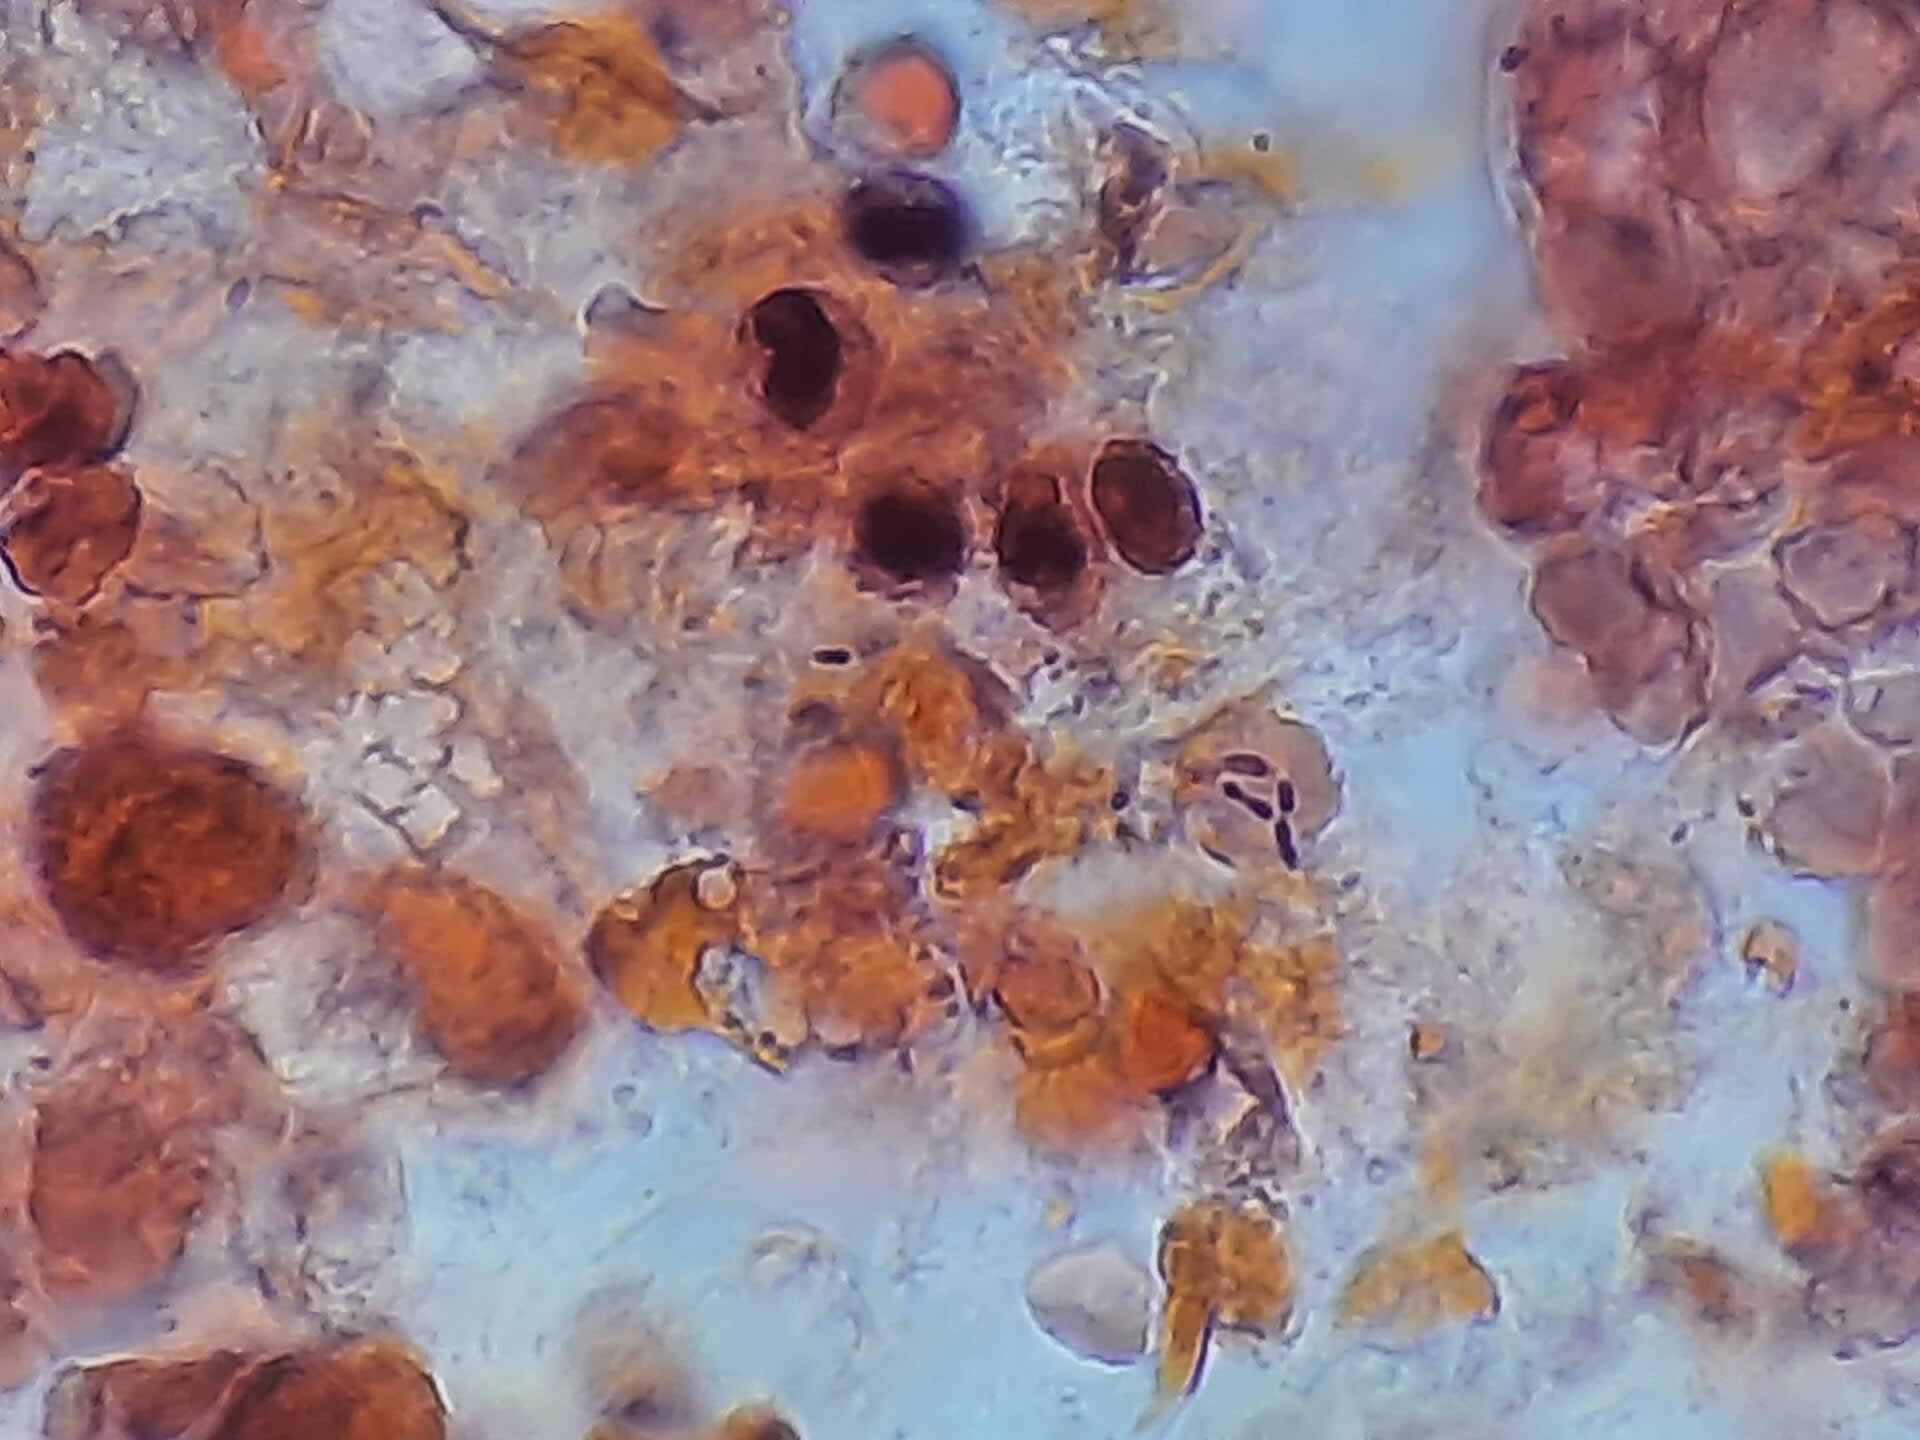
A 6-year-old boy has had recurrent sinopulmonary infections since infancy, including four episodes of the organism stained in the BAL. Flow cytometry shows absent CD19+ B cells in peripheral blood. Serum immunoglobulin levels are markedly reduced across all isotypes. A mutation in a non-receptor tyrosine kinase critical for B-cell maturation is identified. Which of the following best explains why this patient is specifically susceptible to encapsulated bacterial infections?
Ajay Kumar Chaurasiya, CC0, via Wikimedia Commons
Answer: B. X-linked agammaglobulinemia (XLA) results from loss-of-function mutations in Bruton's tyrosine kinase (BTK), a non-receptor tyrosine kinase essential for pro-B to pre-B cell transition in the bone marrow, leading to near-complete absence of circulating B cells and severe panhypogammaglobulinemia. Encapsulated bacteria such as Streptococcus pneumoniae, Haemophilus influenzae, and Neisseria meningitidis resist phagocytosis because their polysaccharide capsules prevent direct neutrophil recognition; opsonization with IgG antibodies is required for efficient Fc receptor-mediated phagocytosis. Without IgG, patients cannot clear these organisms effectively. Option A is incorrect; T-cell lineage is unaffected in XLA, and encapsulated bacteria are extracellular. Option C is incorrect; NK cells target virus-infected and malignant cells, not capsule-expressing bacteria. Option D is incorrect; complement deficiencies primarily predispose to Neisseria specifically, and the capsule is not a complement target per se. Option E is incorrect; dendritic cell function is intact in XLA.
Source: McDonald, C., et al. (2021). The role of Bruton's tyrosine kinase in the immune system and disease. Immunology, 164(4), 722–736.
Your next questions are ready.
The question bank picks up from here: it adapts to what you just missed and brings it back right before you'd forget it.
Why is ampicillin added to empiric meningitis coverage for elderly patients?expand_more
Listeria monocytogenes causes meningitis predominantly in neonates, elderly (>50 years), pregnant women, and immunocompromised patients. Listeria is intrinsically resistant to all cephalosporins (ceftriaxone will not cover it). Ampicillin is the drug of choice for Listeria. The standard empiric regimen for these groups is ceftriaxone + vancomycin + ampicillin. TMP-SMX is an alternative if PCN-allergic.
What is Waterhouse-Friderichsen syndrome?expand_more
Waterhouse-Friderichsen syndrome is bilateral adrenal hemorrhage caused by meningococcal septicemia (N. meningitidis bacteremia). The meningococcus triggers DIC and endothelial damage, causing hemorrhage into the adrenal glands, leading to acute adrenal insufficiency. Clinically: fulminant bacterial sepsis + petechial/purpuric rash + bilateral adrenal hemorrhage on CT + hypotension unresponsive to vasopressors. Treat with antibiotics + stress-dose corticosteroids.
Study smarter with a short weekly email. No spam — unsubscribe anytime.
✓ You're in — talk soon.
Reading is one thing. Remembering is another.
Turn this guide into questions you’ll actually remember
Progress Note turns concepts like this into adaptive questions and spaced review, so difficult topics come back to you exactly when you’re about to forget them.